THOUGHTS ON:
Training, Rehabilitation,
&
Best Care Practices

New Year - New Goals: Setting & Achieving Your Goals This Year.
If you are like me, you love to set goals, spend hours on action plans to achieve those goals, and ponder on the impact and improvements you can make to yourself, your company, your family, your health, and everything else around you.
Fast forward from when we originally posted this blog, it is now 2020! Wow!
If you are like me, you love to set goals, spend hours on action plans to achieve those goals, and ponder on the impact and improvements you can make to yourself, your company, your family, your health, and everything else around you.
While you will not find a shortage of articles telling you how to set goals. Or how by February 1st, over 80% of people will have already abandoned their resolutions, let’s just keep this short and to the point in hopes that you are aiming to be part of the 20% who holds on, pushes through, and progresses not just your life, but your family’s, and everyone you interact with.
When gearing up for the new year, or getting back on track, set your aim high and work these 3 steps.
BE SMART
We have all heard of the ‘SMART’ acronym about goal setting.
Specific: Be as specific as possible with your goals, they are easier to break up and achieve if they are clearly defined.
Measurable: This is usually the easiest part. How will you know when you have achieved your goal? When you hit your mark. 1000 miles running - $100K in growth - 2 full weeks of vacation time with your family. Put a number to it!
Attainable: Don’t make your goals too easy. Set your goals just at the end of your reach. Goals that make you work and dig down deep create the best feelings of accomplishment when completed.
Relevant: Is this goal important to you? Does it help you become a better person? Can accomplishing this goal help and serve others?
Time-Based: Every goal must have a deadline, or it is just a thought; a dream; an everyday task.
Break down each goal you have set into smaller, workable, SMART pieces.
THE ONE THING - BUILD YOUR FOUNDATION
Studies have shown that we are incapable of multi-tasking! Don’t believe me, just try to do three things at once and see how well they are completed, if at all. The new year brings about much excitement about the possibilities and opportunities ahead, but if our focus shifts to too many things at once, it will all quickly fall apart. Start by reading ‘The One Thing’ by Gary Keller and focus all of your attention on one goal at a time. See it through to completion and then move on to the next.
When I sit down to plan out my year, quarter, or week, I review my One Thing, that big goal for the year. But, it has to be broken down further than that. Humans simply can’t focus on one thing for an entire year! You know the saying, ‘The way to eat an elephant is one bite at a time,’ it’s true. If you want to reach your BIG goal, break it down.
I have shifted my life, personal and professional, to ROCKS. This isn’t a fancy acronym, but I do like to think of these rock as the material needed to build the foundation of what I hope to achieve and provide to the world during my life. ROCKS are 2-3 small steps that can be taken each 90 days that move you a step closer to your ONE BIG THING. Science has shown us that the extent of our ability to focus on a task is 90 days, so this method works perfectly. Break your big goal down into 10-12 steps and put all your focus into 2 or 3 of them every quarter.
This works the same in business as it does running—every quarter, you have to change cycles. You may want to run a 3:30 marathon this year. You have four macrocycles of training to complete this year, each composed of 2-3 microcycles. Just going out and haphazardly running will not get you to your goal, you have to plan and focus.
10X EVERYTHING
Look at your goals. Look at the energy, time, commitment, and focus it will require, and 10 X it! In Grant Cardone’s ‘The 10X Rule’, he discusses that anything worth accomplishing will require ten times more time, energy, and resources than you initially thought. How do you attack this, with massive action.
In summary, take an hour this week, work through your goals and develop an action plan. Assure they are SMART, begin by focusing on just one, and TAKE MASSIVE ACTION!
- Happy New Year -
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management. If you have an injury that is preventing you from doing the things you enjoy, call or schedule now.

Hamstring Injury - Part 1: Anatomy & Runner's Risk
It’s the start of a beautiful day. You were able to get to the track around 6:00 am for a solid speed workout, your favorite. You warm-up, go through your stretching and dynamic movement routine, and besides a little early morning stiffness, you feel great. Then it happens, you are on number 5 or 12 200 meter repeats, and the back of your leg cramps up something fierce! You stop, stretch, massage, but nothing helps…now you can’t run - workout over.
It’s the start of a beautiful day. You were able to get to the track around 6:00 am for a solid speed workout, your favorite. You warm-up, go through your stretching and dynamic movement routine, and besides a little early morning stiffness, you feel great. Then it happens, you are on number 5 or 12 200 meter repeats, and the back of your leg cramps up something fierce! You stop, stretch, massage, but nothing helps…now you can’t run - workout over.
If this sounds familiar, you know that hamstring injuries are terrible. They are hard to predict, difficult to treat, and can sideline a running longer than a stress fracture. As distance runners, this is a less common injury when compared to Runner’s Knee, Shin Splints, and IT Band Syndrome…but they can be much more complicated and stubborn to bounce back from.
As a Salt Lake City-based runner myself, I have had a few minor (luckily) hamstring injuries back in my hurdling days. Now, as a primarily distance runner, spending more time on the trails of the Wasatch Mountains, my hamstrings have felt strong and resistant to stress. But as we will discuss in this series, that doesn’t mean it can’t all go south tomorrow.
If you have ever watched a runner IMMEDIATELY pull-up in a race and can see the grimace on their face; you can almost feel their pain. If you have been unfortunate enough to experience this yourself, you don’t want to ever think about that moment again…so let’s move on!
We are here to take a deep look at and discuss hamstring injuries. What they are, how they happen, the different types of hamstring injuries we experience as runners, what you can do about them, how to rehab a hamstring injury, what the return to running process looks like, and eventually how we can prevent a dreaded hamstring injury.
Hamstring Anatomy & Function
Hamstring Anatomy Review
Before we dive in to the function of the hamstring, how it responds during the running gait, and the injuries common among the running group, lets have an anatomy review, shall we?
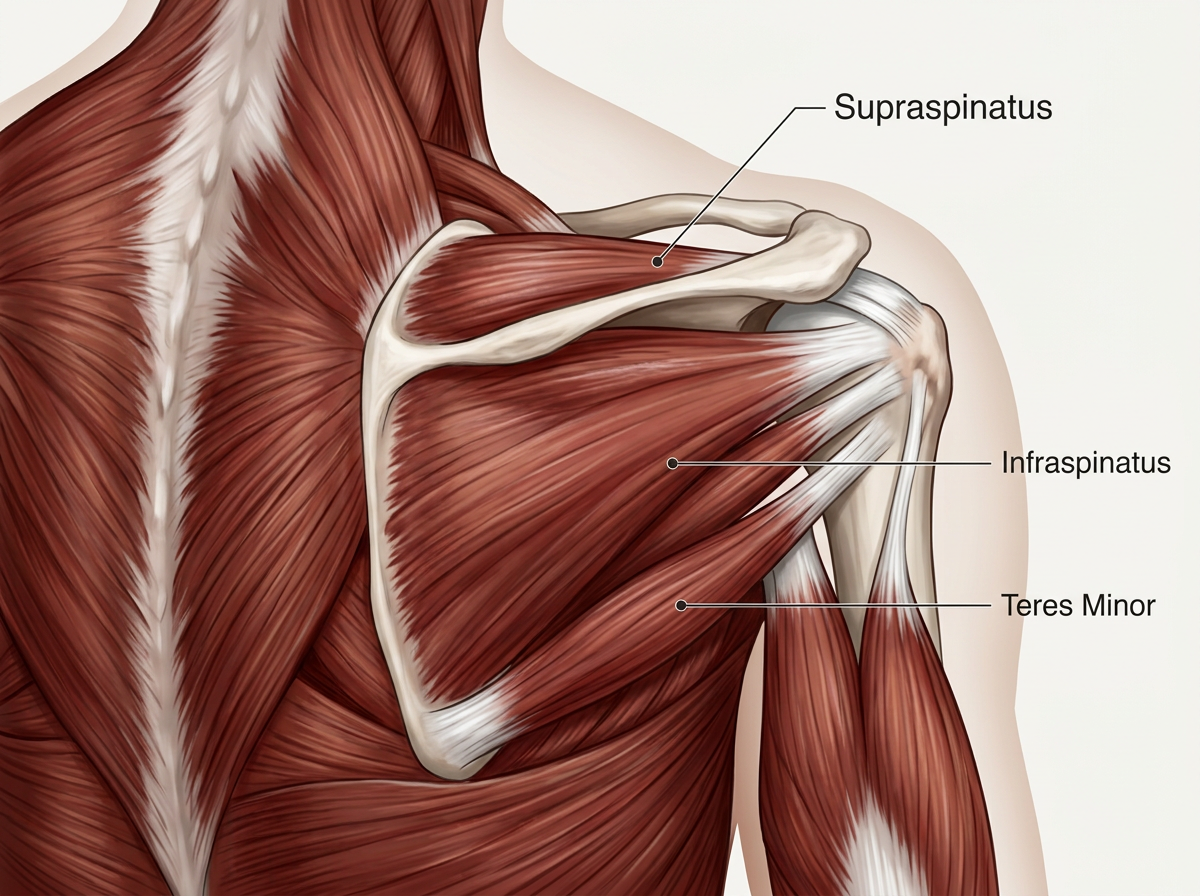
The hamstring group is made up of 3 muscles, one of which has two heads, meaning we have 4 areas to concern ourselves with. The muscles and their actions are as follow:
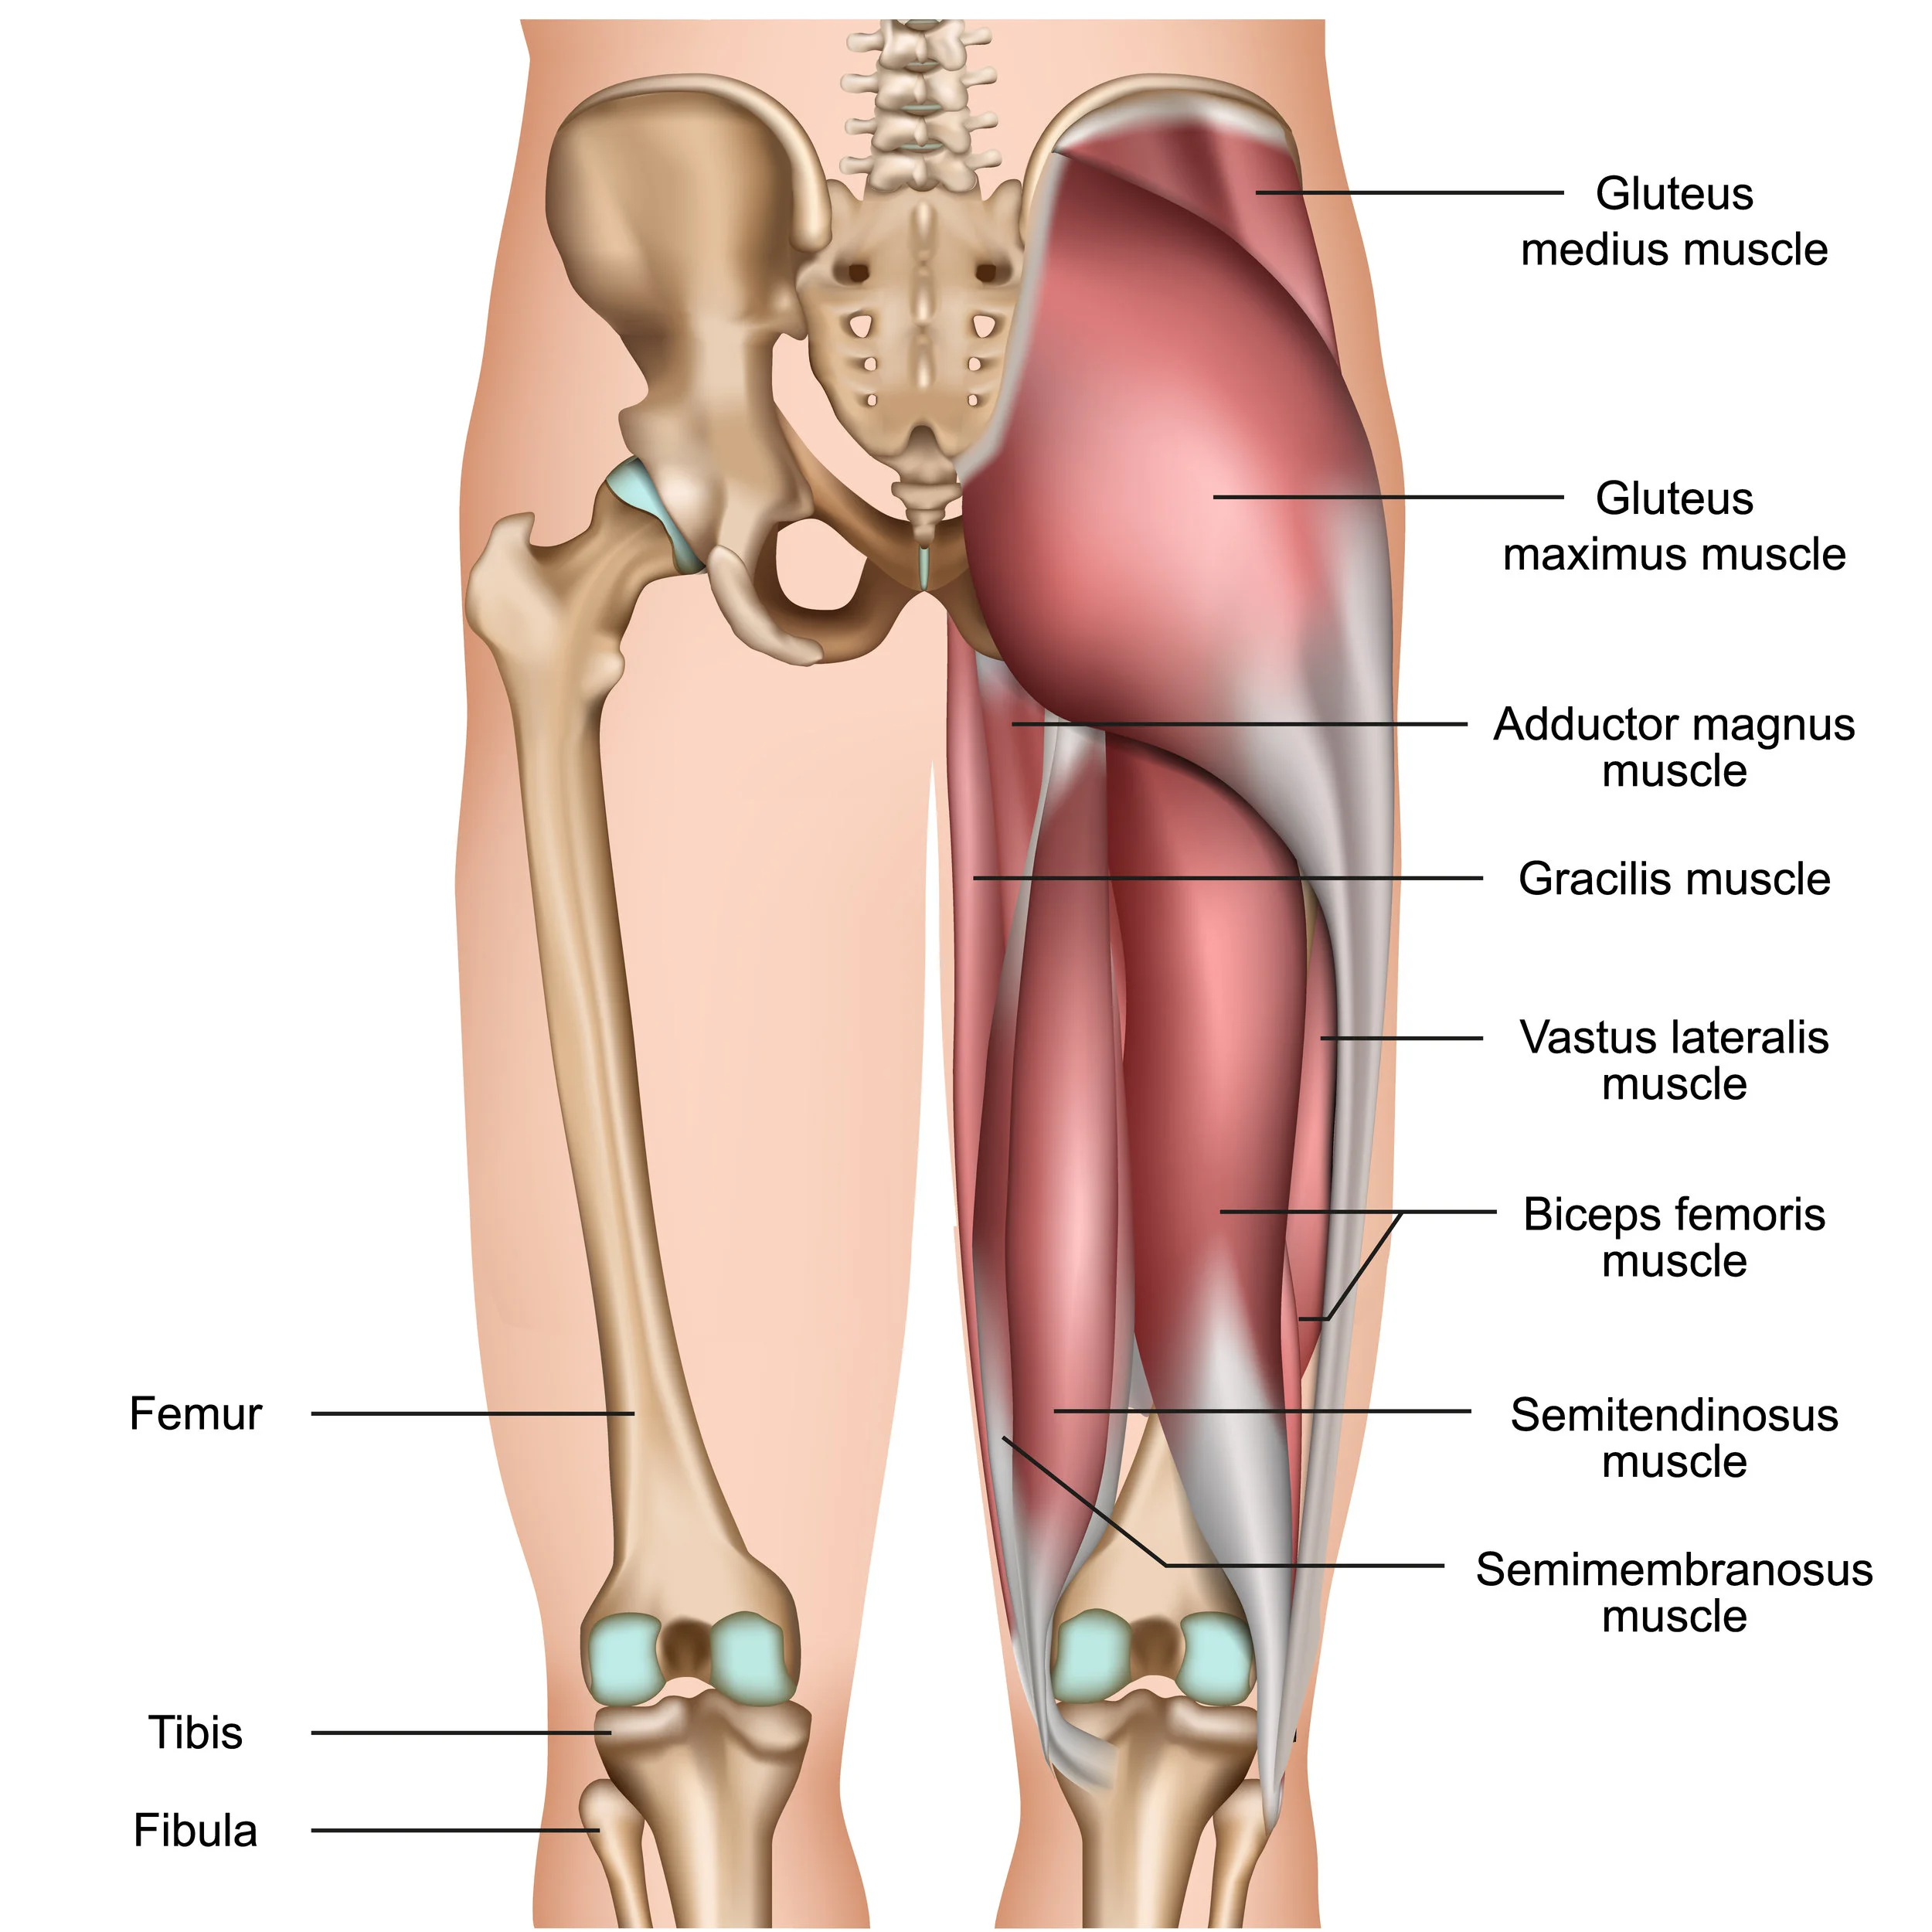
Semitendinosis: The semitendinosis mucles originates from the ischial tuberosity (sit bone) and inserts below the knee on the medial side of the tibia. This orientation causes it to act on two joints meaning it is both a Knee Flexor and Hip Extender. Due to its insertion on the inside of the tibia bone, it can internally/medially rotate the tibia when the knee is bent and also internally rotate the femur when the knee is extended.
Semimembranosis: The semimenbranosis muscle originates and inserts very closely to the semitendinosis and acts similarly as a knee flexor and (poor) hip extender. There are subtle differences in the two ‘semi muscles’ but it’s claim to fame is more along the lines that is may play a role in knee stability given it is suspected to have a functional relationship with the popliteus muscle on the back of the knee and a few fibers supporting the MCL. We learn more about the body everyday, so this may change.
Biceps Femoris: The Biceps Femoris has a similar function as the ‘Semi muscles’ in that it assists in knee flexion, and lower leg deceleration during the runners gain cycle, but it is somewhat special. The biceps femoris muscle has two heads that attach to two different places. The long head comes all the way from ischial tuberosity like the ‘semi brothers’, crossing the hip joint, making it a hip extender. But the short head, it comes off the back of the femur at a spot called the linea aspera. The short head does not cross the hip joint so it does not extend the hip, but it does have a special power. If you are unfortunate enough to experience an avulsion of the hamstring origin off the ischial tuberosity, the short head is still attached and allows you to, albeit weakly, flex the knee. This allows you to maintain some ability of ambulation. Our bodies are smart!
Basic Function Of The Hamstrings In Running
The hamstrings have a very important role in the running gait cycle, but it may not be what you think. As distance runners, our hamstrings are not as strongly used as in our sprinting counterparts, but as we all know after a good speed work session, they are back there serving ther purpose.

To keep this simple. The hamstrings job is to ‘slow’ down the leg as it swings forward. WHAT? SLOW DOWN? Yes! And the faster you run, the harder it works to slow down the leg.
It does this in what is called an eccentric contraction. Simply put, the hamstring fires as the leg swings forward so that your foot and lower leg do not go flying out, causing the knee to fully extend, and then you land on a locked knee. This would cause many injuries, and runners with a lack of control here often have knee and hamstring injuries.
Okay, so lets go a little deeper…nerd-out if you will.

For a great review of the gait cycle, check out the Biomechanic.
When the leg is planted in the stance phase, the hamstring contracts with the quads and adductors to create a stable platform inwhich we can use our momentum to continue to propel forward.
As the leg moves into the toe off phase, the hamstring supports by contracting more concentrically aiding in the push-off that propels us forward..but here is where it gets fun.
During the mid part of the swing phase, the hamstring is passive as the quads and adductors do most of the work bringing the leg foward. The hamstring does work to pull the heel toward the butt in good form, but they do more stretch than anything as studies suggest the hamstring stretches from 50% length to 90% length during this time.
Once we start moving from mid swing to heel contact, the hamstring kicks in eccentrically, and puts the brakes on the lower leg, allowing for a stable platform to land and maintain during the new stance phase.
What Do The Hamstring Do For Distance Runners?
As distance runners, we work through all of theses running phases, just less draumatically than our explosvie sprinter friends. The hamstrings act more in the stability and concentric role during our long outings, which leads way to one theory as to why distance runners deal with more tendinopathy injuries (generally overuse) than strains and avulsion injuries (dynamic and powerful contractions).
What Types Of Hamstring Injuries Do Runners Experience?
Acute Hamstring Strains In Runners:
This is one of the most common overall injuries to plague athletes, for running, it is usually a problem for the sprinter of the group. A muscle strain, or pulled muscle, occurs when a muscle is suddenly overstretched, resulting in the tearing of some of the fibers within the fascicles that make up the larger muscle as a whole. This can be a very small percentage which only causes mild tightness, to a more prominent injury that can range from mild swelling, to complete immobility with bruising and severe swelling.
As a runner, if you are to experience a hamstring injury, a mild strain is preferable. Typically, we can get back out and perform modified running in 2-4 weeks with full healing and return to play in 4-8 weeks.
Hamstring Tendinopathy In Runners:
This is what we see most. As distance runners, we typically run far, make us prone to overuse injuries. Those injuries typically start with a little tightness that goes unaddressed because we are able to continue running. Over time, that muscle tightness begins to place an overload on the tendon, and that tendon begins to get irritated. In can inflame, dehydrate, become sensitive, and eventually make it difficult to run, walk, or sit for long periods.
There are two places this can occur, the lower tendon insertion, which we typically see acutely after a race, fall, or a big downhill effort. This area is often where we see a rupture in sprinters. If you have ever watched a 100m or 200m race and seen a running pull up very quickly and then fall or start hopping, this is what they experienced, and it can be career-ending at the highest level of the sport.
Now, for the upper tendon origin. High hamstring tendinopathy is so common and so frustrating, it has been listed in the runner’s guide of forbidden phrases. High hamstring injuries suck…there is no way around it. These injuries take TIME and often require some time off from running. I told you it was a forbidden term.
High hamstring tendinopathy typically takes 3-6 months for a full recovery and complete release to high volume and high intensity running. Care involves a strict plan for in-office and home care…and even with that, we still send out a good percentage for co-management with an orthopedist.
To summarize this injury. Don’t ignore your hamstring tightness or an injury you believe to be a mild strain. Give it attention, seek help, and rest if necessary. Unfortunately, some runners will press on, and the outcome is very unfortunate.
Hamstring Avulsion Injuries In Runners.
This is a tough one that typically requires surgical intervention. An avulsion injury is when the hamstring tendon pulls away from its attachment on the bone and takes part of the bone with it. These are uncommon without a significant mechanism of injury, we don’t typically see this from just running, but it has happened. This injury will cause severe pain, swelling, and bruising and should be examined by an orthopedist as soon as possible as the muscle can begin to ‘roll-up’ and atrophy shortly after the injury.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.
If you are in the greater Salt Lake City, Utah area and are a runner dealing with a nagging hamstring injury, we are here to help. Click the link below to schedule a consultation appointment and lets get you back out and running.

Spinal Manipulation - Who Benefits Best From This Effective Treatment Option
Spinal manipulation, or the chiropractic adjustment, is the hallmark of Chiropractic Medicine, but what population of patients benefit from this safe and effective treatment option?
Spinal manipulation, the hallmark of Chiropractic Medicine….

First -> Let’s address the elephant in the room! Spinal Manipulation has been touted to help or heal everything from low back pain to the common earache and yearly influenza epidemic. While many practitioners, and patients alike, claim that a chiropractic ‘adjustment’ cured all their ills, current research does not support those claims. We are not here to call those cases out as some people honestly did find an improvement to their conditions through spinal manipulation, we just can not provide consistent results to a large number of subject to clearly understand the mechanism.
However; Low Back Pain, Neck Pain, Muscle and Joint Injuries, Strain/Sprain Injuries…we have mounds of data to support the effectiveness of manipulation and manual therapy in these cases. So much, that we can now predict who will benefit best from this type of care.
What Does Spinal Manipulation Look Like?
Before we jump into what we call ‘Clinical Prediction Rules’ regarding joint manipulation, please realize that each person is an individual, and each condition is as unique as the person who presents with it. Utilizing these rules is not the end all be all; there will be outliers. Some people have tried joint manipulation, or exercise, or dry needling, or a myriad of other therapies with little to no results. Sometimes their condition is passed this type of intervention and needs to bypass conservative care for more invasive options. Moreover, many of these patients either receive ONLY ONE therapy or had the wrong ‘concoction’ of care for their condition, or the phase of healing they were in when the therapy was used was incorrect causing poor timing to be the culprit of poor outcomes. So…if you have tried a few of these, don’t give up and completely write them off. Get a second or third option, look at it with a set of fresh eyes and try a new direction, a new order of care and see how your condition improves.
Now, back to the predictions. Below are what we consider to be the characteristics of patients who research predicts will have the best and fastest outcomes from spinal manipulation.
The Number Of Days With Your Current Low Back Complaint is LESS THAN 16 Days.
Pain & Radiation Of Symptoms (Pain, Numbness, Tingling) Does Not Go Farther Than The Knee.
Fear Avoidance Behavior Assessment. You Do Not Fear That Your Back Pain Will Last Forever and Will Not Keep You From Enjoying Life In The Future.
Through Examination, Movement Assessment, and Provider Palpation, At Least 1 Spinal Segment of the Lumbar Spine is Restricted/Hypomobile.
At Lease 1 Hip Has More Than 35 Degrees of Internal Rotation.
So What Does This Mean?
If you present to an office like ours with ACUTE LOW BACK PAIN that is RADIATING PAIN TO THE GLUTES, RESTRICTED LUMBAR SPINE ROM, and ONE HIP HAS RESTRICTED INTERNAL ROTATION ROM…

YOU ARE A GOOD CANDIDATE FOR SPINAL MANIPULATION
&
WE SHOULD ANTICIPATE GREAT RESULTS.
Two studies on spinal manipulation, utilizing these Clinical Prediction Rules found:
Patients who presented with less than 4 of the 5 above rules, had a 45% likelihood for a positive response from spinal manipulation.
Positive Response means that after 2-3 treatments with spinal manipulation, patients saw a 50% reduction in symptoms and pain.
A patient who presented WITH at least 4 of the 5 rules, increased their likelihood of a positive outcome to 95%.
Another study, utilizing a side-lying lumbar manipulation technique along with ROM exercises, found a 50% reduction in symptoms in 11 of 12 participants. The one participant who did not respond still found a reduction in symptoms, but did not reach the 50% reduction mark the study considered as a ‘positive outcome.’
In summary, Spinal Manipulation is an effective and safe tool for low back pain. But it is just that, a tool! Care that relies on only one treatment modality will only be somewhat useful to a specific, and small, population. Care that focuses on the patients' individual presentation and goals, and adapts a variety of therapies for that particular condition will typically yield the best results. If you have tried manipulation, PT, massage, dry needling, or any other therapy as a stand-alone treatment option, I invite you to give us a call to see how we can develop a better treatment plan around your personal goals.

Resources:
Cleland, JA et al. The Use of a Lumbar Spine Manipulation Technique by Physical Therapists in Patients Who Satisfy a Clinical Prediction Rule: A Case Series. JOSPT 2006.
Flynn, T et al. A Clinical Prediction Rule For Classifying Patients With Low Back Pain Who Demonstrate Short-Term Improvement With Spinal Manipulation. Spine 2002.
Childs, JD et al. A Clinical Prediction Rule To Identify Patients With Low Back Pain Most Likely To Benefit From Spinal Manipulation: A Validation Study. Annals of Internal Medicine 2004.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Sciatica Pain Relief Part 2: Common Causes of Sciatica
In part 1 of our Sciatica Pain Relief series, we covered the basics of sciatica, sciatic nerve pain, and the general anatomy involved. While this may not interest everyone, it is useful in understanding the sharp, burning, and often debilitating pain that radiates down the leg that some people experience with low back pain. Our goal in this series is to inform, empower action, and give our fellow Salt Lake City, Utah friends the information and tools to help yourself through this condition as well as the understanding of when to seek care and a trusted source to do so if needed. In part 2, we are going to briefly discuss some of the most common causes of sciatica but before going forward, check out part 1 by clicking the button below.
In part 1 of our Sciatica Pain Relief series, we covered the basics of sciatica, sciatic nerve pain, and the general anatomy involved. While this may not interest everyone, it is useful in understanding the sharp, burning, and often debilitating pain that radiates down the leg that some people experience with low back pain. Our goal in this series is to inform, empower action, and give our fellow Salt Lake City, Utah friends the information and tools to help yourself through this condition as well as the understanding of when to seek care and a trusted source to do so if needed. In part 2, we are going to briefly discuss some of the most common causes of sciatica but before going forward, check out part 1 by clicking the button below.
TOP 5 COMMON CAUSES OF SCIATICA
1) Disc Buldge - Intervertebral Disc Compression
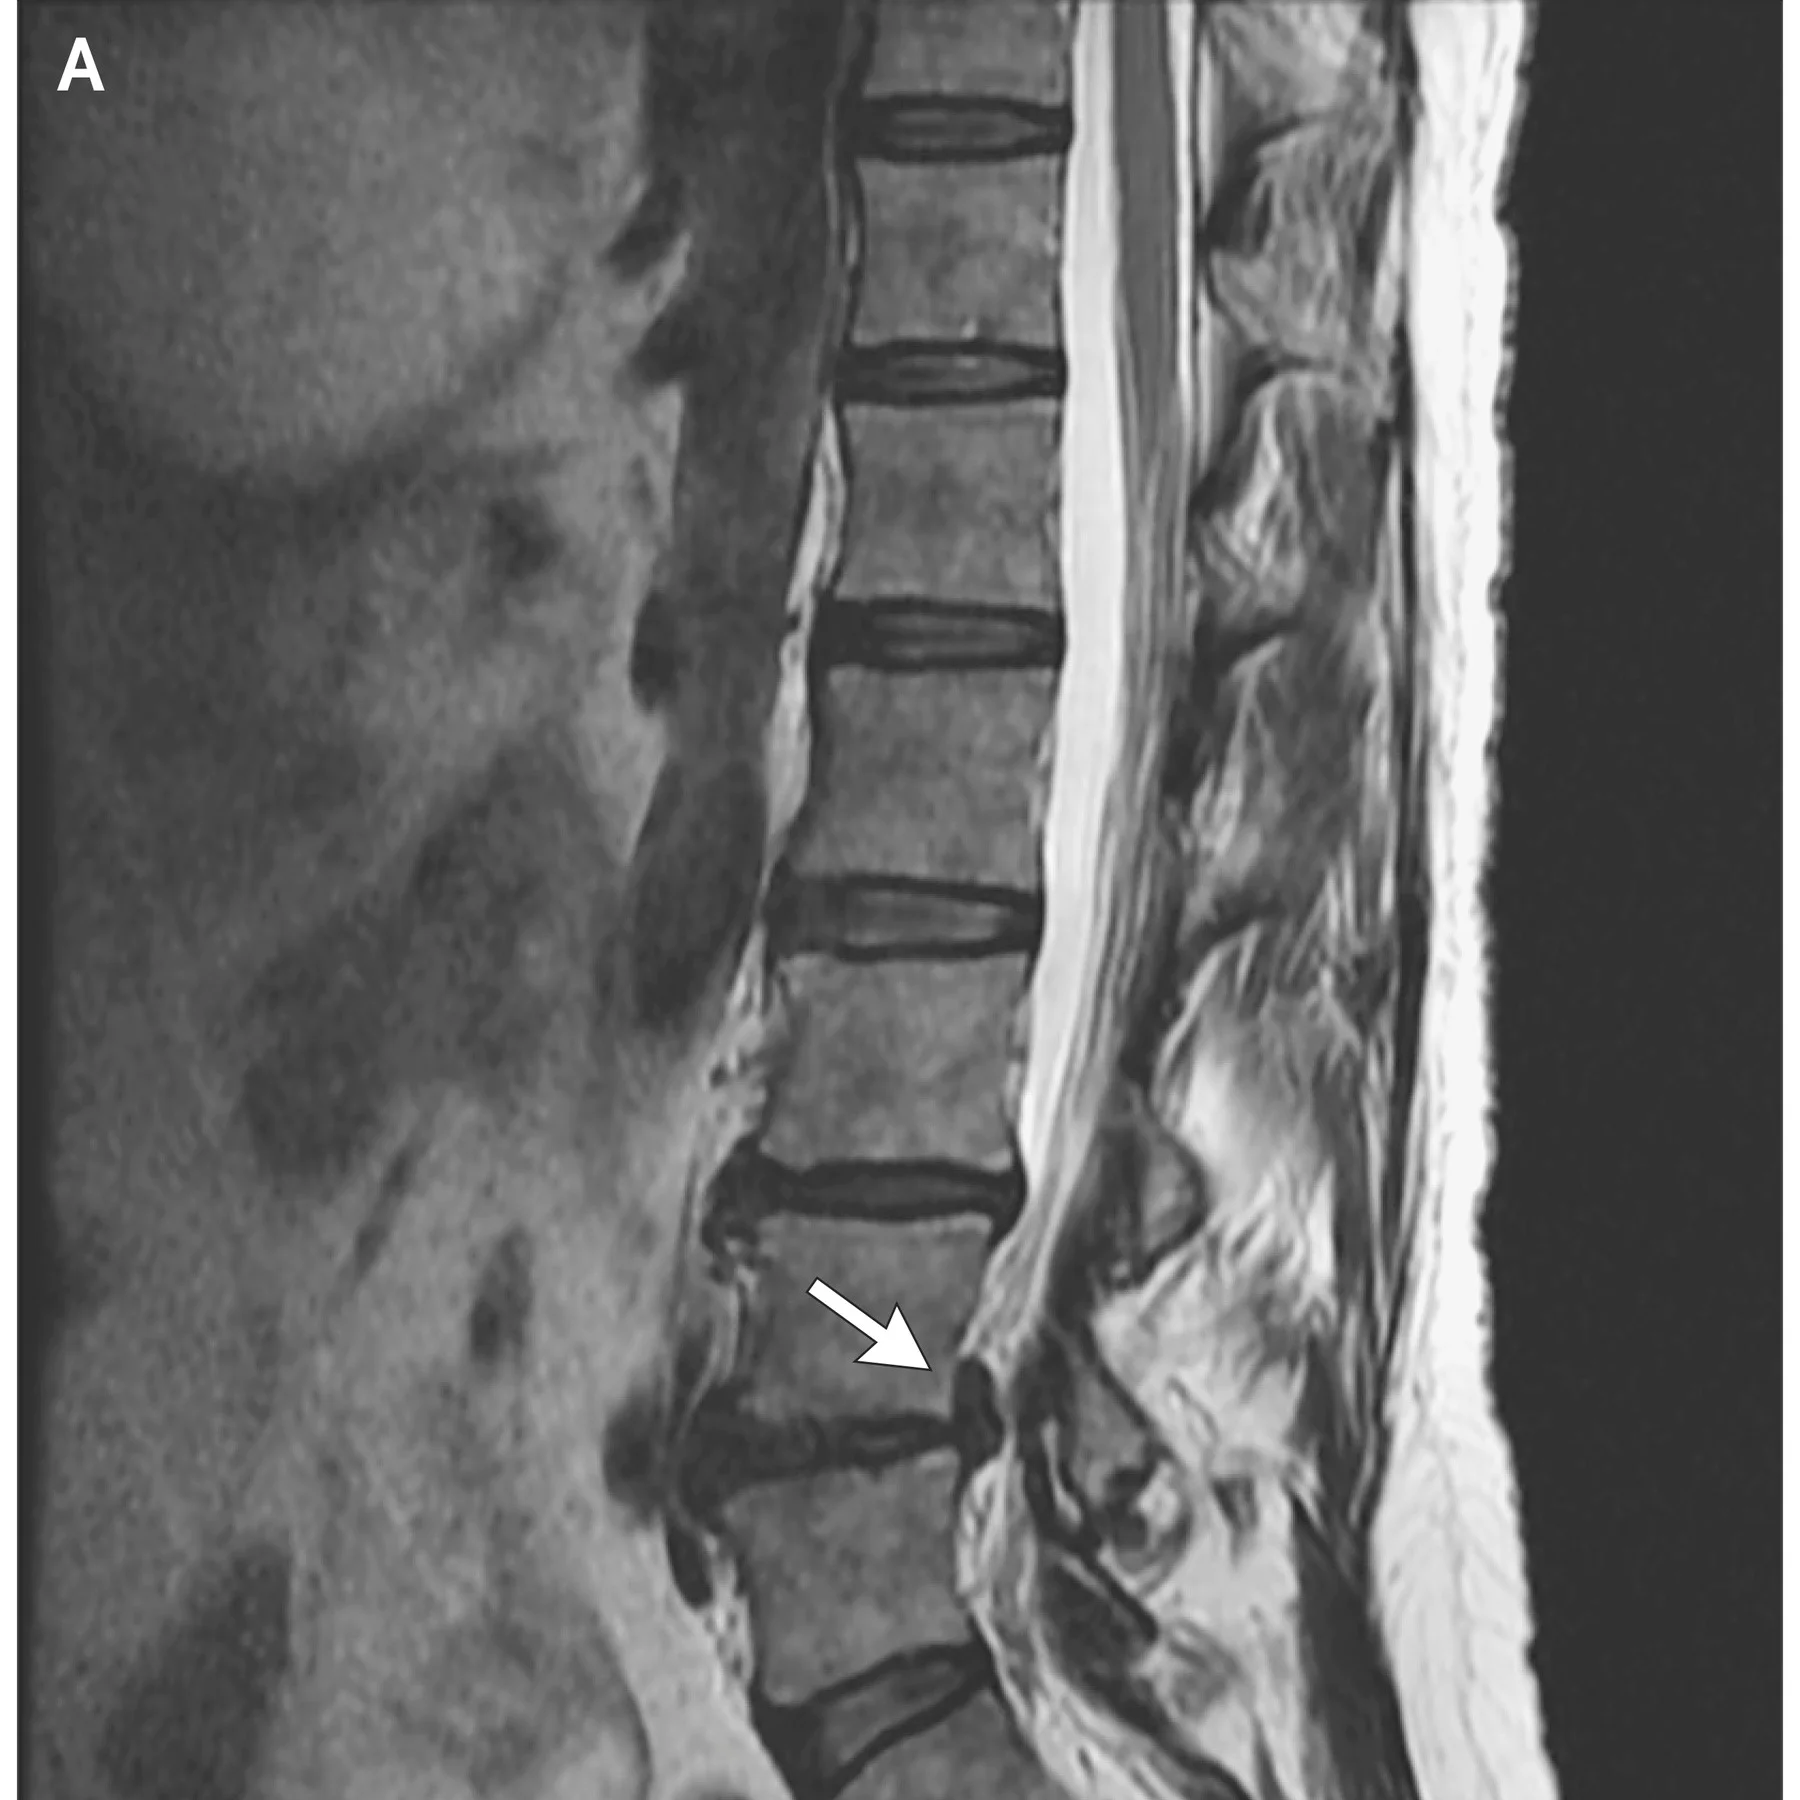
Credit: Allan Ropper, M.D., Ross Zafonte, D.O. Sciatica Review Article. New England Journal of Medicine
Starting with the most common cause makes sense as this is what most literature supports and what most people fear when they have some incident or trauma that leaves them with sciatic nerve pain shooting down their leg. A disc bulge is just that, an outpouching, or bulge, of the disc (compressive and supportive tissue between each vertebrae that acts as a shock absorber and allows for movement of the spine) which then presses up against the spinal cord or a nerve as it exits the spinal column. Compression here can be mild to severe, bringing with it anything from pain, numbness, and tingling, to complete weakness of the muscles and limb supplied by the nerve being compressed.
Note: If you are experiencing the latter of those, please seek help immediately as progressive weakness is a red flag and often requires immediate imaging and intervention.
Now, the debate is out on this as disc, and other lumbar spine pathologies are considered somewhat normal. Chances are, before the injury or event that left you feeling this way, the disc bulge was ALREADY PRESENT! This event just aggravated it enough to cause pain.
For Review: Check out the chart in this article we did on spinal imagining and what the best, most current research supports. You will find that most people are walking around with ‘back issues’ with absolutely no pain or quality of life disruption.
THREE THINGS TO KNOW ABOUT SCIATICA & DISC ISSUES
You are not your image. Chances are, your MRI will show things that were already present and may not be the primary source of your sciatic nerve pain.
A true disc injury and resulting sciatica take time to heal. The body will do most of the work. Chiropractors and therapists are here to help with symptoms, function, and assuring you are in the best position to heal. There is NO magic pill for this, TIME heals.
If you are experiencing sudden weakness or progressive numbness that does not let up, seek care immediately as intervention is most likely needed to assure permanent damage is not experienced.
2) Lumbar Spine Stenosis - Canal & IVF Narrowing

Similar to a disc bulge, Sciatica related to Spinal Stenosis is a physical compression of the nerve roots that make up the sciatic nerve. However, this is more of a slow growing, progressive problem. In most cases, these do not wake up in severe pain overnight, these patients report constant discomfort, on-again-off-again radiation of pain, slow loss of range of motion, and typically do not have a time or event to relate a start of the pain.
As we age, the spine and discs degenerate. In the disc, this happens by a loss of height, dehydration, and loss of flexibility of the tissue. In the spine, and other high-stress bone and joint areas, degeneration happens by bone growth, bone spurs, and rigidity of the joints. This degeneration can cause enough of a response that bone will grow around areas where nerves pass from the spinal cord to the rest of the body (Intervertebral foramen or IFV) taking an already small space and slowly closing it down.
3) Piriformis Syndrome - Posterior Hip Tightness
We hit on this at length in the first part of our sciatica series. The relationship between the sciatic nerve and the piriformis muscle is well established. Most people have a sciatic nerve the tracks superficially (toward the surface) over the top of the piriformis muscle or just inferior to it. However, there is an appreciable percentage of the population where the sciatic nerve or a branch from it, pierces the middle of the piriformis muscle. It is believed to be the main culprit of 2-12% of sciatica pain with research on both sides stating over and under-diagnosis. Either way, anatomical and occupational variants are common causes of sciatic nerve pain as well as low back pain.

Credit: Allan Ropper, M.D., Ross Zafonte, D.O. Sciatica Review Article. New England Journal of Medicine
4) Double Crush Syndrome
Double Crush Syndrome, many of the cases we see fall into this category. Let me explain.
A patient presents after a fall, accident, or just a bad nights sleep with a chief complaint of sciatica with low back pain. An exam reveals a limited range of motion in the lumbar spine, tightness of the muscle in the posterior hip, namely the piriformis muscle, and numbness and tingling down the leg. Let's say that an MRI was ordered and it revealed a mild to moderate disc bulge.
Crush One - The disc bulge, assumed to be caused or irritated by the incident, it mildly compressing the nerve. Crust Two - In response to this injury, the body goes into defense mode and muscles begin to tighten, namely those of the posterior hip.
The initial compression at the spinal level causes a 3/10 pain, when you add in the tightness and compression at the hip, the patient is now up to a 7/10 pain with shocks of pain during specific movements. This is a Double Crush.
As with most, the disc issue is hard to affect with treatment directly, but focus can be directed toward the hip muscles, proper movement of the area and exercises to help with mobility and pain are prescribed, bringing the person back down to a 4/10 pain and allowing them to maintain most daily activities while the disc heals…remember, TIME heals discs.
5) Pregnancy
While this is not a diagnosable cause of Sciatica, sciatica is a very common complaint from expecting mothers. The cause here can be as elusive as any other, but pregnancy, the position of the baby, and the mothers specific size, anatomy, and lifestyle habits and experience with sciatica pain before the pregnancy. While there are many unknowns here, sciatica pain typically affects mothers-to-be in the latter half of the pregnancy, and most will respond to conservative care.
RED FLAGS

Sciatica is a very well described condition. The direct cause can be challenging to uncover, but there are a few things to be aware of if you are suffering from sciatic nerve pain. If you are experiencing any of the below items, we suggest you seek care immediately to assure the condition does not cause long term issues and to direct you to the right healthcare provider. Most cases can be managed conservatively (Chiropractic, Physical Therapy, or At Home) while others require medical intervention (injections, imaging, or surgery).
Progressive neurological symptoms. If you are experiencing numbness, tingling, or weakness that is worsening, please seek help from a trained provider.
If your injury is the result of a fall, auto accident, or home/work accident, consulting with a healthcare provider will help rule out any significant issues and speed our recovery.
As with other serious low back injuries, if you experience any loss of bowel or bladder control, this is an immediate ER referral.
If you have have been dealing with sciatica for more than 1 week without any relief, it is time to get help. Most self-resolving injuries and pain will let up after a couple days.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

New Year - New Goals: Running To Better Health
Improved health tops nearly every new year's resolution list ever made, 2019 will be no different. From this, running comes to the forefront of our ‘get in shape’ plan because of its ease (almost everyone can shuffle one foot in front of the other, not saying it is easy) and relatively low cost (a decent pair of shoes and some running gear is all you need). While this plan seems fool-proof, there is a reason 60%+ of the people we see in our clinic are runners, new and old.
Improved health tops nearly every new year's resolution list ever made, 2019 will be no different. From this, running comes to the forefront of our ‘get in shape’ plan because of its ease (almost everyone can shuffle one foot in front of the other, not saying it is easy) and relatively low cost (a decent pair of shoes and some running gear is all you need). While this plan seems fool-proof, there is a reason 60%+ of the people we see in our clinic are runners, new and old.

While running seems easy to do, there are many things to consider. Are you a runner? Have you ran since high school, or ever? Did you know your body type matters? Can you cover 1-2 miles and not be in misery the next day? Do you have good shoes? Do you have a partner to run with, accountability is essential for follow-through? You didn’t think about any of that, did you? While we will have more running and running-related injury articles to share with you in 2019, let’s start with some current research (Nerd-Alert).
Who:
In this study, the authors gave 914 novice runners a GPS watch and tracked them over a year to study their habits and direction of their running habits. The group was divided into 3 groups based on their BMI (Normal, Overweight, & Obese) to help determine if there were any differences and similarities in their training selection.
What They Found:
The first interesting finding was that in this self-guided exercise program, all categories selected similar training doses. The authors suggest that this may explain the higher injury risk among overweight and obese runners compared with normal-weight runners.
Normal weight runners ran faster and farther than their overweight and obese counterparts. This is anticipated as these are all novice runners, but the perceived effort was not established and could be an interesting metric to develop.
Suggestions:
Starting a new exercise program is exciting, but one must also be willing to understand and see that they are at a starting point. Novice runners are at high risk of injury if they start too fast, or do too much too soon. An initial dose of high volume can lead to an injury that causes you to become inactive, losing any benefits you sought to gain in the first place.
BMI is important to consider. Have a higher BMI does not mean you can or should not run, it means that the programming must be different. Training has to do with ‘load,’ and by that, we mean that if you are 200 lbs, it is a bit more challenging and harder on your body to run 3 miles than for someone who is 150 lbs. This changes as we continue training and adapt, but at first, we must take things slow.
Any activity is better than a sedentary lifestyle! Remember to take things slowly. Your body will be sore, but that is to be expected. If you have pain, or your soreness lasts longer than a few days after exercise, seek professional guidance on preparing your body and running programming.
Who:
The authors of this study followed 447 runners over a 24-week running program. Their goal was to determine the risk associated with high-intensity running plans and high-volume running plans.
Before the study began, they hypothesized that runners on the high-intensity program would have higher rates of Achilles tendinopathy, calf injuries, and plantar fasciitis while runners on the high-volume program would experience more runners knee, iliotibial band syndrome, and patellar tendinopathy.
What they found:
Over the 24-week training program, 80 runners sustained an injury. However, the authors found no difference in the risk of injuries related to training volume or intensity.
Suggestions:
The others suggest this discrepancy between these results and other related studies and running-related injury beliefs are related to the periodization of the running schedules, the scheduled running intensities, and the categorizations of injuries.
Runners or all shape, sizes, and abilities will eventually run into injury. Prevention by adhering to a solid warm-up routine, frequent attention to weaknesses and immobilities, while also modifying a training plan to one's abilities can help prevent injury.
When beginning a new running plan, or increasing your volume or intensity, it is suggested to do one at a time. Listen to your body and take time off as needed.
If you are taking up running again, or for the first time, and you have questions, we are here to help. Running injuries are common. You often do not have to stop running, just a rework and refocus of your training plan. Train Hard & Train Smart.
Happy & Healthy 2019!
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Resolve Low Back Issues Part 7: What Happens When You Need To Seek Care?
Our intention with this series on Low Back Pain has been to inform and empower you, or your loved ones, to take action and realize that movement can help, as well as, prevent low back pain. That your low back pain is not a life sentence.
Care & Rehab For Low Back Pain
Supporting The Greater Salt Lake Valley. Helping You Get Back To The Activities You Enjoy.
Our intention with this series on Low Back Pain has been to inform and empower you, or your loved ones, to take action and realize that movement can help, as well as, prevent low back pain. That your low back pain is not a life sentence.
While all of this information is useful and should be utilized before, during, and after a Back Pain episode, the reality is that some people will need to seek care.
You have had a front-row seat to one pillar of our care, the education and exercise component. When seeking care for low back pain, putting your faith solely in one person, and relying on them for everything is not advised and will severely hinder your progress.
YOU (YES, YOU) HAVE TO PUT IN THE WORK, TIME, & EFFORT!
As a Sports Chiropractor that treats low back pain every single day…we see it time and again in our patients… If home care is not adhered to and a person does not take their situation seriously and put in the effort, back pain will take forever (or it seems that way) to resolve.
Today we are going to give you another up-close look at our care process, this time what we actually do here in the office. Our goals are to (1) Determine the cause of your pain/injury (2) Provide care in the office that helps you toward your goal of running, golfing, sleeping, moving again…pain-free, and (3) Give you the tools and education to help yourself.
We structure our care around 3 pillars: Soft Tissue, Joint Motion, Exercise. We have exhausted our opinion and writing on exercise, please refer to parts 1-6 for direction. Now, lets briefly take a look at what care looks like inside the office.
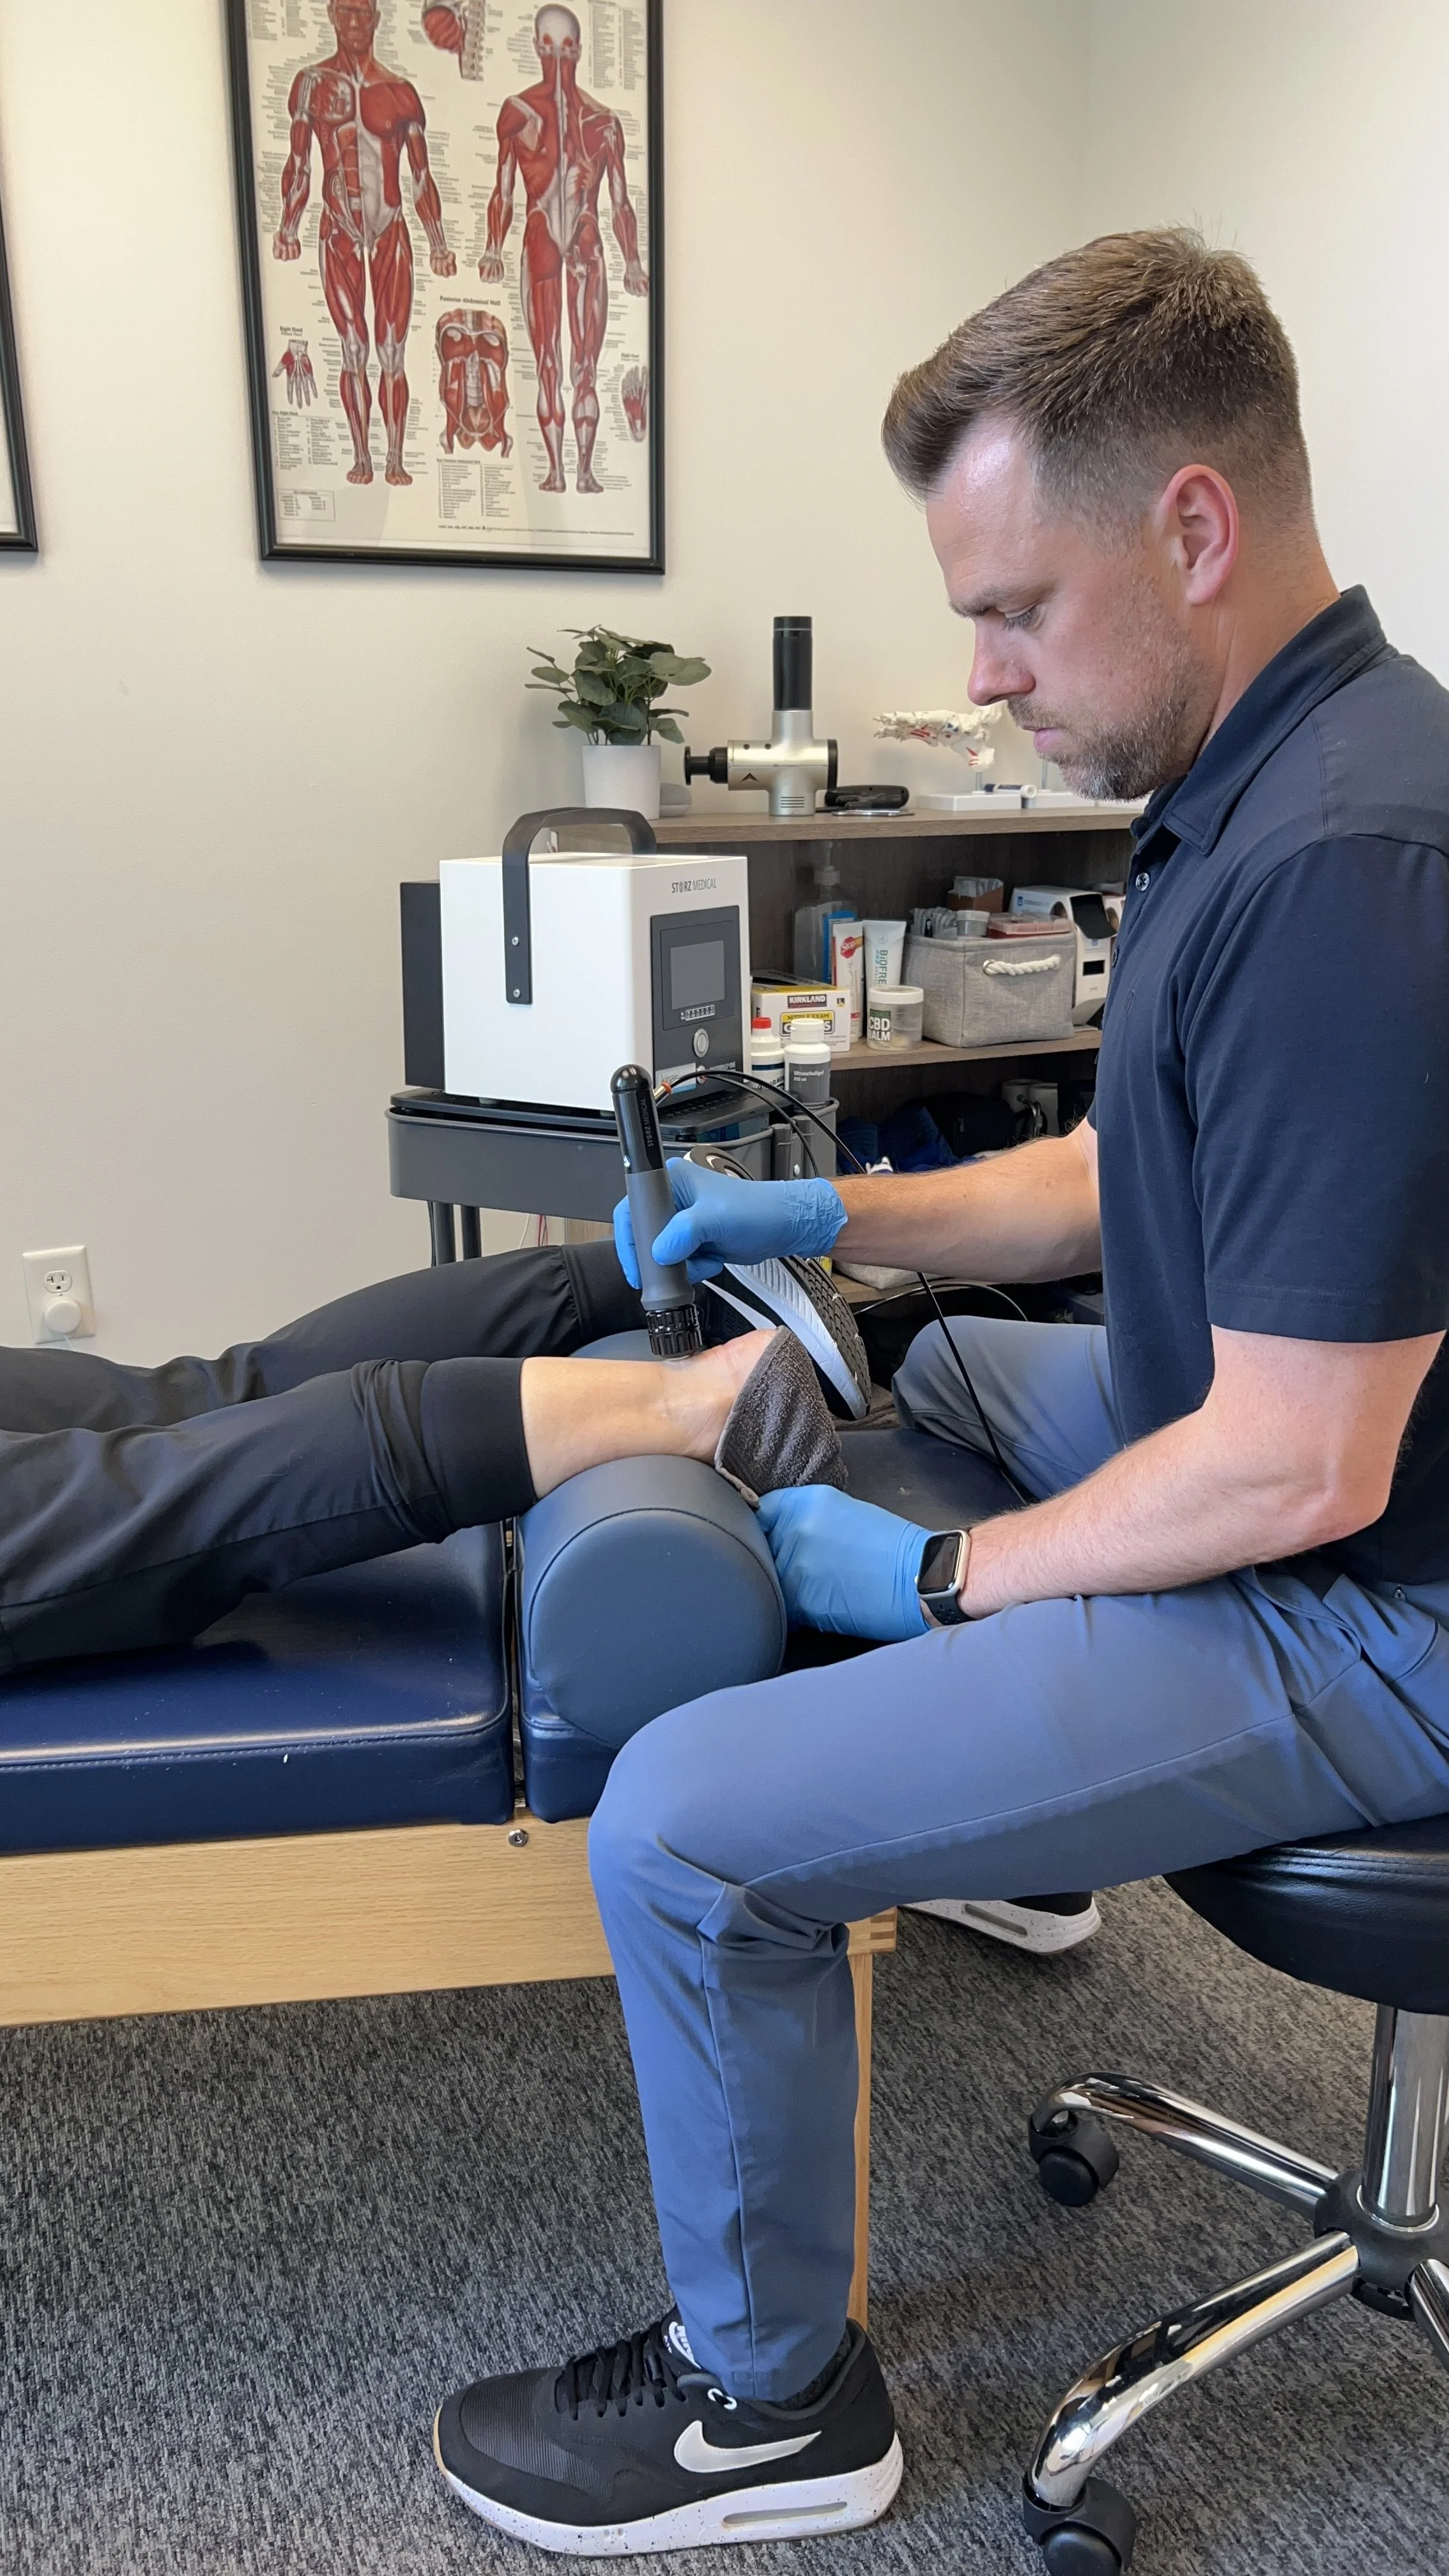
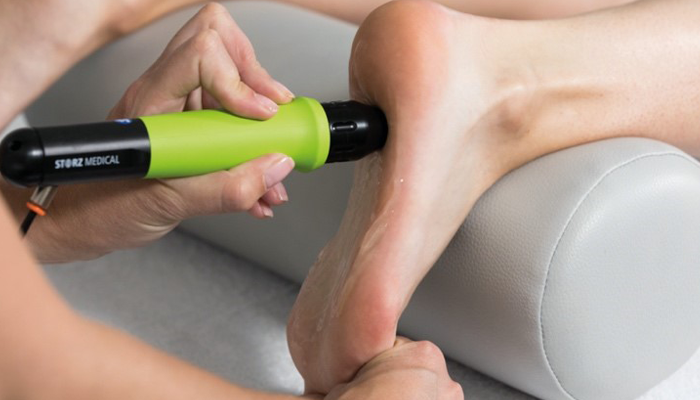
SOFT TISSUE CARE
JOINT MANIPULATION
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Resolve Low Back Issues Part 6: Self-Care - What You Can Do For Low Back Pain
Over the last 5 weeks, we have discussed everything from what low back pain is, most common causes, some of the most common myths associated with low back pain, and when to consider imaging studies (x-ray, MRI, CT) due to red flags that lead us to something more severe being the cause. We even covered a few tips to help when you find yourself traveling for work or vacation.
We have been building up toward the actual care of low back pain but wanted to fully educate on how common low back pain is, what we know about low back pain at this time, and help you focus on life outside of back pain.
Low Back Pain Self-Care
Over the last 5 weeks, we have discussed everything from what low back pain is, most common causes, some of the most common myths associated with low back pain, and when to consider imaging studies (x-ray, MRI, CT) due to red flags that lead us to something more severe being the cause. We even covered a few tips to help when you find yourself traveling for work or vacation.
We have been building up toward the actual care of low back pain but wanted to fully educate on how common low back pain is, what we know about low back pain at this time, and help you focus on life outside of back pain.
Today, we are going to do just that.
When we look to decrease disability from low back pain and encourage and support patients back to an active lifestyle, this is done in two ways. EDUCATION & EXERCISE. We have already discussed the education component. Now it is time for exercise. Below are 5 ways to help manage and prevent your low back pain with exercise and stretching routines that can be done at home, the gym, or even at the office.
Side Bar -> If anyone gives you a hard time, or tosses a laugh in your way for stretching at the office, I will leave it up to you to either invite them to join (because they need to do this too), or, wait until they start having an issue with low back pain and then pass them our card! Seriously though, invite your co-works to join in, make it an office party, it will be fun.
Fix Your Low Back With These 5 Easy Exercises & Stretches You Can Do At Home or Work.
STEP 1: Get Out Of Bed With Our Morning Routine.
After a good night’s sleep, it is common for our muscles to want to remain in bed. Because of this, early morning activities can challenge our bodies more than they are ready to handle, resulting in a nice low back strain injury. If you are already dealing with low back pain, you know that morning stiffness can prevent you from even rolling over, not to mention actually get up out of said bed.
STEP 2: Desk Sitters - Get Up & Move
While things are improving, the seats we subject ourselves too in our cars, on the train, and at the office are just comfortable enough to keep you seated for an extensive period of time, but provide little support to keep you from tightening up in the process. Start this NOW -> Set an alarm on your phone that goes off every 1-2 hours. Walk around the office, hand-deliver a message, and then take 30 seconds and perform these stretches.
STEP 3: Pre-Workout Hip Mobility
We are going to assume you have a daily routine of some exercise? If you do not, reset, and start adding some exercise to your life, no other method is as impactful on helping your low back issues. Once you get to the gym, or home if you prefer, go through a GOOD HIP MOBILITY routine. We know that the more we improve the mobility of our hips, the less our low back has to work…overwork.
STEP 4: Post-Workout Core Strength
The same goes for core strength as hip mobility. The stronger our core, the less our low backs have to work. Now…I don’t mean getting down on the floor and performing a half-hearted set or some sorry excuse for crunch/sit-up type exercise. We are talking functional here. Planks, Side Planks, Plank Rolls, Heavy Farmer and Suitcase Walks, as well as The Big 3.
STEP 5: Strength For Life
Most people who have dealt with low back pain have since, and forever will, shy away from true strength movements. But let me just plug that as humans, you should be able to squat as well as pick something heavy off the ground without fear of hurting yourself. As you work on hip mobility and core strength, you have to start working in squats and dead-lifts. Start with these modifications and work on control and endurance.
Exercise is considered the best medicine for low back pain. While this is true and I strongly support this. Our actual goal with care is to get our patients back to these activities. But often, patients present in enough pain that they are unable to run, ski, bike, weight lift, etc. With that said, most can start with basic stretching and mobility until the pain is relieved. From there, exercise can prevent flair-ups, or at least decrease their intensity and length of the episode. Either way, low back pain has to have a component that includes YOU doing some, if not most, of the work.

Next week we will look at some of the traditional, as well as, new developments in conservative care low back pain. Until then, and if you are craving more reading, check out our ‘12 Ways..’ Tips guide to further help your low back pain.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Resolve Low Back Issues Part 5: You Are Not Your Image. (Red Flags & Imaging Considerations)
In part 4 of our Fix Your Low Back series, we discussed some of the most common myths and misunderstandings around low back pain, care of low back pain, as well as updating some of the old-fashioned thoughts. Today, we are going to discuss imaging and red flags as it pertains to low back pain and a couple of VERY IMPORTANT things you need to know.
Low Back Pain Imaging
Best Practices & The Truth
In part 4 of our Fix Your Low Back series, we discussed some of the most common myths and misunderstandings around low back pain, care of low back pain, as well as updating some of the old-fashioned thoughts. Today, we are going to discuss imaging and red flags as it pertains to low back pain and a couple of VERY IMPORTANT things you need to know.

Imaging is an excellent diagnostic tool, when appropriate, to help ASSURE PROPER care.
Not-so-long ago, a patient would walk into a chiropractic office and get a standard set of x-rays; or they would schedule an appointment with an orthopedic physician and would be required to obtain an MRI before they can be seen.
This standard practice has fortunately been labeled as inappropriate, and national organizations such as the American Chiropractic Association and American College of Physicians have recently taken a strong stance against these practices.
CURRENT BEST PRACTICES
Do not obtain spinal imaging for patients with acute low-back pain during the initial 6 weeks after onset in the absence of red flags.
Imaging should not be utilized to monitor a patient’s progress.
WHAT WE KNOW ABOUT IMAGING NOW
There are two extremely important things to know concerning imaging…
Imaging can be harmful. Radiation aside. Unnecessary x-rays and MRIs can bring to light ‘normal variances’ that are NOT the generator of pain but are easy to blame. This causes what is being referred to as the ‘medicalization’ of low back pain.
Example: Someone presents with low back pain, an image is immediately ordered, it shows a bulging disc or some other skeletal irregularity, and the blame for the complaint is placed on this without further discussion. This patient goes on to think that they are doomed to low back pain forever, that their ‘bad back’ will keep them from enjoying their normal activities, and unfortunately, they end up with a regular dose of over-the-counter and prescription drugs.
Now, this is not always the case, but once or twice each month, a patient with low back pain presents to our office stating that they had a bulging disc in their low back over 10 years ago and have been in constant pain ever since. These cases have more to them than just pain, the overutilization and misuse of imaging lead to fear avoidance and catastrophizing. Both are always present in chronic low back pain!
Through recent studies, we know that to a certain degree, lower spine degeneration and pathology are normal, AND NON-PAIN GENERATING, at almost all ages.

What is so important about this chart? Well….
These numbers represent the percent of specific age groups that had degeneration and disc pathology of the lower back in patients who had NO SYMPTOMS OR COMPLAINTS whatsoever.
Also, this was no small review….this study included over 3100 people!
In review, If we took a pain-free 40 y/o person with NO history of low back pain…
Almost 70% would demonstrate degeneration on x-ray.
50% would show a bulging disc on MRI.
Our take-a-way here… YOU ARE NOT YOUR IMAGE! They can play tricks on your thinking and make your back pain much worse just by you believing that what your image is showing is the end all be all of your pain.
With that aside, we do need imaging. WHEN INDICATED THROUGH A PROPER EXAM! Imaging is great for ruling out serious pathology.

RED FLAGS
Red flags are indicators that let physicians know there might be something more serious going on. This can come from a simple history and exam and they demand attention and should be considered before care of any kind is provided. With that said, here is a small list of ‘Red Flags’ common with low back pain complaints.
History of Cancer.
Night Pain.
Progressive Neurological Symptoms & Weakness.
Pain Following Trauma (Fall, Auto Accident, etc.)
Sudden Loss of Bowel or Bladder Function.
Recent Weight Loss.
New Back Pain With Fever.
Failure of 4-6 Weeks of Conservative Care.
History of Recent Fracture of Suspected Fracture.
Family History & Signs of Osteopenia & Osteoporosis.
In summary, and I hate to keep harping on this, but your imaging results may not be as important as they are made out to be in regards to uncomplicated, and even chronic, low back pain.
Spinal degeneration, disc bulge, and other pathologies are often normal findings as we age and have not been proven to be pain generators.
Imaging early in the care process in the absence of red flags is NOT in line with current ‘best practice’ suggestions and guidelines.
Studies have shown that a thorough history and exam with your provider can provide information to determine the actual cause of your low back pain.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Resolve Low Back Issues Part 4: Most Common Myths Of Low Back Pain
Few musculoskeletal conditions have a cult-like following of myths as Low Back Pain, many of which have been said by various healthcare providers across all specialties. To help clear the air, let's take a look at the 5 most common misunderstandings and myths that we encounter in our chiropractic clinic that could actually make your low back pain worse.
Low Back Pain Myths
Few musculoskeletal conditions have a cult-like following of myths as Low Back Pain, many of which have been said by various healthcare providers across all specialties. To help clear the air, let's take a look at the 5 most common misunderstandings and myths that we encounter in our chiropractic clinic that could actually make your low back pain worse.
Before we get started…
These myths and misunderstandings are not aimed at making low back pain seem 'made-up,’ it is a very real and challenging condition. These myths are just folklore passed down from old, unsubstantiated in the research, ways of thinking. Our truth is that, if you believe one thing and that makes you feel that your low back is wrecked for life, a long road of pain is what you are in store for. We call this fear-avoidance and catastrophizing, the medicalization of a condition. We will touch more on this when we cover imaging next week. But a big part of recovering from low back pain is believing that you can get better. It may sound silly, but no more ridiculous than believing these myths below!
NUMBER 1: Your back pain is from a misalignment, bone out of place, or a ‘subluxation.’

We don’t practice this way any longer, stop using explanations from this era.
These are common descriptions patients and doctors alike will give when describing their back pain. The most common being...you threw your back out, and it is now misaligned...commonly spoken by chiropractors of a generation ago or current doctors, chiropractors, and physical therapists that have not caught up with current research. The truth to this is that your spine is a dynamic structure designed to move, what we ACTUALLY find is that the pain you are feeling is often associated with immobility, or areas of the spine that should be moving, but due to tight muscles and previous injury, may not be moving well or correctly anymore. Spinal manipulation or an ‘adjustment’ is designed to restore normal motion to these restricted areas.
A bone did not shift out of place and therefore needs to be put back in! That’s not how it works.
NUMBER 2: Arthritis is the root of all evil!

Arthritis is like wrinkles on your face…lets just keep it nice and say they are signs of wisdom. Truthfully, if you live and play hard and long enough, we will all experience some degree of degeneration. However, and please understand this, it is a natural process and does not necessarily equate to pain! When conditions present that are more challenging, using arthritis as the ‘fall guy’ is the easy way out for a provider and an often acceptable answer for the patient.
NUMBER 3: “But…I have scoliosis and a short leg” that is the cause of my back pain.

Just like arthritis, scoliosis and an actual short leg (1cm or shorter than the other) are comfortable areas to place blame when someone presents with back pain. Both can absolutely lead to dysfunction, and if unaddressed, pain and discomfort. To a certain degree, uneven leg lengths and spinal rotation/curvature are normal variants, meaning most people have these at a mild level and are unlikely to be a pain generator. For most (not all) look to place the blame elsewhere.
NUMBER 4: Rest is what I need to recover, right?

The days of ‘take 2 of these, rest, and call me in the morning’ are long gone. You likely have a relative who spent a good amount of their life with back pain that limited some or all of their activity. When you see a case like this or someone who is much too young to be experiencing recurrent back pain, it may seem like the right thing to do is rest up for a while. Fortunately, we now have stacks of research that supports the fact that bed rest is the worst (top 3 at least) idea when it comes to low back pain. The new adage is ‘Movement is Medicine.’ When someone presents to our office, we are not only just trying to relieve pain, but to relieve pain SO THEY CAN GET OUT AND MOVE. Even walking, WALKING, has been shown to reduce low back discomfort and be a great tool to prevent future occurrences.
NUMBER 5: Slap a brace on it & it will be fine.

Brace low back pain long term & you should join the circus with that thinking.
This is excellent advice if you are looking to weaken your core muscles completely. Did you know that powerlifters use the belt to their advantage to complete amazing feats of strength not to brace their low back, but to give their stomach something to press in to, creating intraabdominal pressure (think bracing your stomach if someone was to punch you) that stabilizes the spine from the inside? Our bodies are amazing, it has its own ‘weight belt’ built-in. Using straps, belts, or any other contraption like this for extended periods of time tells your body that you do not need it to do its job anymore. This core weakness and inability to naturally brace yourself through muscle control —> LEADS TO CHRONIC LOW BACK PAIN.
In summary, things change. Our treatment methods and your outlook on your condition must change. Every single one of these five myths is still spouted today in an office somewhere near you. Knowing the validity of that is often more important than the care you receive. While in certain circumstances, these can be valid reasons for low back pain. For most, especially those who come through our Cottonwood Heights, Utah Chiropractic and Rehabilitation clinic, we want a better answer. One that helps address and correct the dysfunction. One that promotes confidence and encourages the patient to try harder, that they can feel better and live a life they enjoy.
Next week, in part 5 of our Fix Your Low Back Series, we are going to discuss red flags, when you need imagining, and why you shouldn’t always rest your diagnosis and pain on those images.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Resolve Low Back Issues Part 3: Most Common Cause Of Low Back Pain & What You Can Do About It.
In part one of our ‘Fix Your Low Back’ series, we discussed the 3 categories of back pain; Functional, Structural, and Pathological. As we learn about low back pain, we find that these groups interact with each other frequently. Essentially, these are medical definitions used to categorize your low back pain, but let’s step back and take a look at how your everyday actions could be the primary cause of your discomfort.
As an example, let’s say you sit at a desk for 8 hours each day. From here, you head to the gym where you like to lift weights and improve your cardio. It has been shown that repeatedly lifting heavy objects with a rounded spike (functional), can lead to disc bulges (structural). For many, we just hit the nail on the head as to where your back pain is coming from, for others, we are going to dive into the most common’s and discuss how a simple change in activity can make all the difference.
The Most Common Causes Of Low Back Pain
In part one of our ‘Fix Your Low Back’ series, we discussed the 3 categories of back pain; Functional, Structural, and Pathological. As we learn about low back pain, we find that these groups interact with each other frequently. Essentially, these are medical definitions used to categorize your low back pain, but let’s step back and take a look at how your everyday actions could be the primary cause of your discomfort.
As an example, let’s say you sit at a desk for 8 hours each day. From here, you head to the gym where you like to lift weights and improve your cardio. It has been shown that repeatedly lifting heavy objects with a rounded spike (functional), can lead to disc bulges (structural). For many, we just hit the nail on the head as to where your back pain is coming from, for others, we are going to dive into the most common’s and discuss how a simple change in activity can make all the difference.
THE THREE MOST COMMON CAUSES OF LOW BACK PAIN
While our cohort population is small, we have found that low back pain presenting to our chiropractic clinic in the Salt Lake City, Utah valley typically falls into three categories:
SEDENTARY LIFESTYLE & WORK ENVIRONMENT
Studies show that people sit on average, 8 hours per day, with some sitting upwards of 15 hours. Honest question...do you sit with good posture? I know I don’t! After 5-10 minutes, I feel like I am hunched over. As a result of this, the muscles of our hips and pelvis begin to tighten and the muscles of our core begin to disengage. This leads to what is called an anterior pelvic tilt which prevents a neutral and happy spine, causing abnormal compression and stress on the disc and excess strain on the low back muscles as they over engage trying to perform the job of the core and hip muscles, essentially causing what we call Lower Crossed Syndrome. It is said that sitting is the new smoking, this may not be exactly true, but I get the reference. Either way, you look at this, the truth is that we have to get up off your butt, move, and do it often.

Solutions To A Sedentary Work Environment
Walk to deliver messages instead of using email.
Take the stairs and park farther away.
Halfway through your morning and afternoon, get out of your chair and perform the following
Wall Push-Ups x 10
Body Weight Squat x 10
Hip Flexor Lunge Stretch x 10
Plank x 30 seconds
BUTT & GUT SYNDROME
The Butt & Gut Syndrome has developed out of the sedentary lifestyle. When we sit for long periods of time, day in and day out, we are unable to use the muscles of our Butt & Gut efficiently. If you are sitting on your glutes (butt) all day, they are unable to contract, the same goes for our core when we sit hunched over a keyboard/desk/cell phone all day. This weakening of the main supporting cast of our lower spine causes the muscles of the back to overwork as it is now doing the job of these weakened muscles when you are walking, running, cycling, lifting weights, gardening, or just sitting on the couch. Simply put, you have to get your core ACTIVE!

Solutions To Help Your Sedentary Home-Lifestyle:
Walk with family after dinner.
Perform the TV challenge - 10 Reps each of Push-ups, Sit-Ups, and Body-Weight Squats EVERY commercial break.
IMMOBILITY & STIFFNESS
Not only does sitting for long periods weaken muscles, but it can also lead to stiffness above and below the low back area. Many of us have felt the pain between our shoulder blades, or feel like our hips just don’t move like they once did…you know….back in our prime. Did you know that this stiffness can come from a low back issue, but more times than not, this is the root cause of the problem? When we have stiffness through the middle back and hips, the low back must adapt from a stable environment to act as a mobile environment, something it should not do and is very dangerous to your overall wellbeing and function. When the low back compensates for other areas of joint stiffness, problems can and will occur.

Solutions To Help with Immobility & Stiffness:
Start or increase the amount you walk each day.
Develop a stretching routine you can maintain.
Lift weights, run, swim, play tennis, take up yoga, just do something that makes you move!
Improve your mobility with one of these routines.
Have you started noticing the pattern here yet? If you have picked up on the fact that we sit too much, and activity as simple as walking can bring lasting relief, you are correct. A recent study in the Journal of Disability Rehabilitation showed that walking was effective in improving pain, disability, quality of life, and fear-avoidance among chronic low back pain sufferers. With that said, I want to end part 3 of this series with a light of hope…
…most back pain is treatable and preventable!
Stay tuned for part 4 of our fix your low back series. We will be discussing common myths that need to be cleared up as well as red flags that must be addressed before treatment can begin.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.