THOUGHTS ON:
Training, Rehabilitation,
&
Best Care Practices

Exercise Rehab for Knee Osteoarthritis: Managing Movement & Preventing Flare-Ups
This is the final article in our four-part series, and in many ways it’s the most important. If Part 3 was about relieving pain and restoring movement, Part 4 is about the piece that keeps you moving for years to come: exercise rehabilitation. It’s worth reminding you that exercise doesn’t “fix” osteoarthritis, because established cartilage and bony changes aren’t reversible. But exercise is the single most effective way to manage the condition, reduce pain, keep the joint functioning, and prevent the flare-ups that derail daily life. That’s not a clinic opinion; it’s the consistent conclusion of the research.
Why Exercise is First-Line Care for Knee Osteoarthritis
Every major clinical guideline for knee osteoarthritis places exercise at the center of treatment, ahead of injections and surgery for most people. 2 The reason ties back to Part 1 of our blog series: osteoarthritis reflects a mismatch between the load on a joint and its capacity to handle that load. You can’t easily lower the demands of daily life, but you can raise the joint’s capacity to handle it, and that’s exactly what exercise does. Stronger muscles absorb force, better control distributes load more evenly, and a joint that moves regularly stays healthier than one that’s protected into stiffness.
Systematic reviews and network meta-analyses consistently show that exercise therapy reduces pain and improves physical function in knee OA. 1 The effects are comparable to what many people hope to get from medication, without the side effects, and unlike a pill, the benefits compound as you get stronger. 4
What Kind of Exercise Actually Helps Knee Osteoarthritis?
One of the most reassuring findings in the research is that there is no single “magic” exercise. Strengthening programs, aerobic exercise like walking or cycling, and mind-body movement such as tai chi have all been shown to help, and no one type is clearly superior for everyone. 1 That means the best program is the one that fits your body, your goals, and your life, the one you’ll actually stick with.
• Strengthening: The muscles around the knee and hip, like the quadriceps, hamstrings, glutes, and calves, are your knee’s shock absorbers. Building them is a cornerstone of knee OA rehab. 1
• Aerobic / low-impact conditioning: Walking, cycling, and swimming improve fitness, help with weight management, and keep the joint moving without excessive impact.
• Range of motion and control: Gentle mobility and balance work restore comfortable movement and reduce the sense of stiffness and instability.
• Progression: Load is the key when it’s dosed correctly; we start where you are and gradually build, which is how capacity actually grows.
“But Won’t Exercise Wear My Knee Out?”
This fear keeps many people from doing the very thing that would help them most. The evidence is clear that appropriate exercise does not accelerate osteoarthritis; it protects the joint. Some discomfort during or after exercise is normal and usually settles; a common guideline is that mild soreness that fades within a day is acceptable, while sharp or escalating pain means we adjust the plan. The goal is steady, tolerable loading, not pushing through significant pain.
It’s also normal for progress to be non-linear. Building strength and calming a sensitized joint takes weeks to months, and how much you improve depends partly on factors like your starting strength and consistency. 3 This is exactly where guided rehab helps: we adjust the dose, troubleshoot setbacks, and keep you moving forward instead of guessing.
Managing Knee Osteoarthritis Flare-Ups and Staying Ahead of Them
Even with a good program, knees with osteoarthritis can flare, leading to a period of increased pain and swelling, often after a spike in activity or a change in routine. A flare is not a sign of damage or failure; it’s a signal to temporarily modify, not to stop entirely. During a flare-up, we typically reduce load rather than eliminate movement, use the hands-on tools from Part 3 to settle symptoms, and then rebuild. Complete rest tends to backfire by feeding the deconditioning cycle we described in Part 1.
The most important variable for long-term success is consistency. The benefits of exercise for knee OA fade when you stop, so the goal is a sustainable routine that becomes a permanent habit rather than a short-term “program” you finish and abandon. 3 Combining ongoing exercise with the strategies from earlier in this series; weight management, smart load management, and periodic hands-on care as needed, gives you the best odds of keeping pain low and staying active for the long run. 5
Putting the Whole Program Together
Across four articles, we’ve reframed knee osteoarthritis from an inevitable breakdown into a manageable, whole-joint condition you can actively influence. You understand the anatomy and mechanism (Part 1), the risk factors and prevention (Part 2), and the hands-on care that relieves pain and restores movement (Part 3). Exercise rehab is what ties it together and carries you forward. At Revive Sport & Spine, we build individualized rehab plans that meet you where you are and grow with you so your knee supports the life you want to live.
Key Takeaways
✓ Exercise is a first-line, guideline-recommended treatment for knee osteoarthritis, not an optional extra. 2
✓ Strengthening and aerobic exercise reliably reduce pain and improve function; the best exercise is one you’ll actually keep doing. 1 4
✓ Exercise manages OA and prevents flare-ups; it doesn’t “fix” the joint, and that’s okay. 4
✓ Consistency matters more than intensity; benefits fade if you stop, so long-term habits win. 3
Want a knee rehab plan built for your body and your goals, not a generic handout? Our team designs progressive, guided programs and adjusts them as you improve, so you can manage your knee osteoarthritis with confidence and keep doing what you love.
Frequently Asked Questions About Knee Osteoarthritis
What are the best exercises for knee osteoarthritis?
Strengthening the quadriceps, hamstrings, glutes, and calves, combined with low-impact aerobic activity like walking or cycling, has the strongest evidence. No single exercise type is clearly best, so the ideal program is one tailored to you that you’ll do consistently. 1
Can exercise make knee osteoarthritis worse?
No. Appropriately dosed exercise protects the joint rather than wearing it out. Mild soreness that settles within a day is fine; sharp or worsening pain means the plan should be adjusted. 4
Does exercise cure knee osteoarthritis?
It doesn’t reverse the joint changes, but exercise is the most effective way to manage the condition by reducing pain, improving function, and preventing flare-ups. Think of it as ongoing management, not a one-time fix. 2 4
How long until exercise helps my knee?
Many people notice improvement within a few weeks, with continued gains over months as strength builds. Results depend partly on consistency and your starting point, which is why a guided, progressive plan works best. 3
What should I do when my knee flares up?
Reduce load rather than stopping completely, use symptom-calming care as needed, and rebuild gradually. Complete rest usually backfires by weakening the muscles that support the joint. 3
REFERENCES
1. Exercise Therapy for Knee Osteoarthritis: A Systematic Review and Network Meta-analysis. 2023. https://pmc.ncbi.nlm.nih.gov/articles/PMC10280533/
2. Bannuru RR, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. 2019;27(11):1578-1589. https://pubmed.ncbi.nlm.nih.gov/31278997/
3. Holden MA, et al. Moderators of the effect of therapeutic exercise for knee and hip osteoarthritis: a systematic review and individual participant data meta-analysis. The Lancet Rheumatology. 2023. https://www.thelancet.com/journals/lanrhe/article/PIIS2665-9913(23)00122-4/fulltext
4. Effectiveness of exercise therapy in patients with knee osteoarthritis: an overview of systematic reviews. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC12273085/
5. Anwer S, et al. The Benefits of Adding Manual Therapy to Exercise Therapy for Knee or Hip Osteoarthritis: A Systematic Review With Meta-analysis. JOSPT. 2022. https://www.jospt.org/doi/10.2519/jospt.2022.11062
How We Treat Knee Osteoarthritis: Soft Tissue Therapy, Joint Manipulation, and Shockwave
By now you know the theme of this series: knee osteoarthritis (OA) is a whole-joint condition, and the goal of care is to restore the joint’s capacity to move and load comfortably. Hands-on care plays an important role, especially early on, by calming pain and stiffness enough that you can move, strengthen, and get back to the things you value. At Revive Sport & Spine in Murray, UT, three tools feature prominently in our management of knee OA: soft-tissue therapy, joint manipulation and mobilization, and shockwave therapy. Here’s what each does and what the research says.
Soft Tissue Therapy for Knee Osteoarthritis
An arthritic knee rarely hurts in isolation. The muscles and connective tissue that cross the joint (the quadriceps, hamstrings, calf, and the iliotibial band and hip muscles above) often become tight, guarded, and tender as the body protects a sore and irritated joint. That protective tension changes how the knee tracks and loads, and it can become a source of pain in its own right.
Soft tissue therapy, including targeted muscle release techniques, instrument-assisted work, and myofascial techniques, aims to reduce muscular guarding, improve tissue mobility, and reduce pain sensitivity, allowing the joint to move more freely. Soft tissue approaches have been shown to improve pain and function in knee OA and are low-risk.4 We use soft tissue work not as a stand-alone ‘fix’ but as a way to make movement and loading more comfortable, which sets up everything else we do.
Joint Manipulation and Mobilization for Knee Osteoarthritis
Osteoarthritic knees frequently feel stiff and restricted, and that restriction isn’t only in the main hinge of the knee; it often involves the kneecap, the small tibiofibular joint, and the neighboring hip and ankle. Skilled joint manipulation and mobilization apply controlled, specific movement to these joints to restore glide, reduce stiffness, and improve range of motion.
The evidence here is encouraging, particularly when manual therapy is combined with exercise. A systematic review with meta-analysis found that adding manual therapy to an exercise program produced greater improvements in pain and function for people with knee or hip OA than exercise alone. 1 Broader overviews conclude that manual therapy for the knee is generally clinically effective and safe, while noting that the quality of individual studies varies, a good reason to use it as one part of a comprehensive plan rather than the whole plan. 2 In practice, we use manipulation and mobilization to open up comfortable movement quickly, then reinforce those gains with rehab so they last.
Shockwave therapy for Knee Osteoarthritis
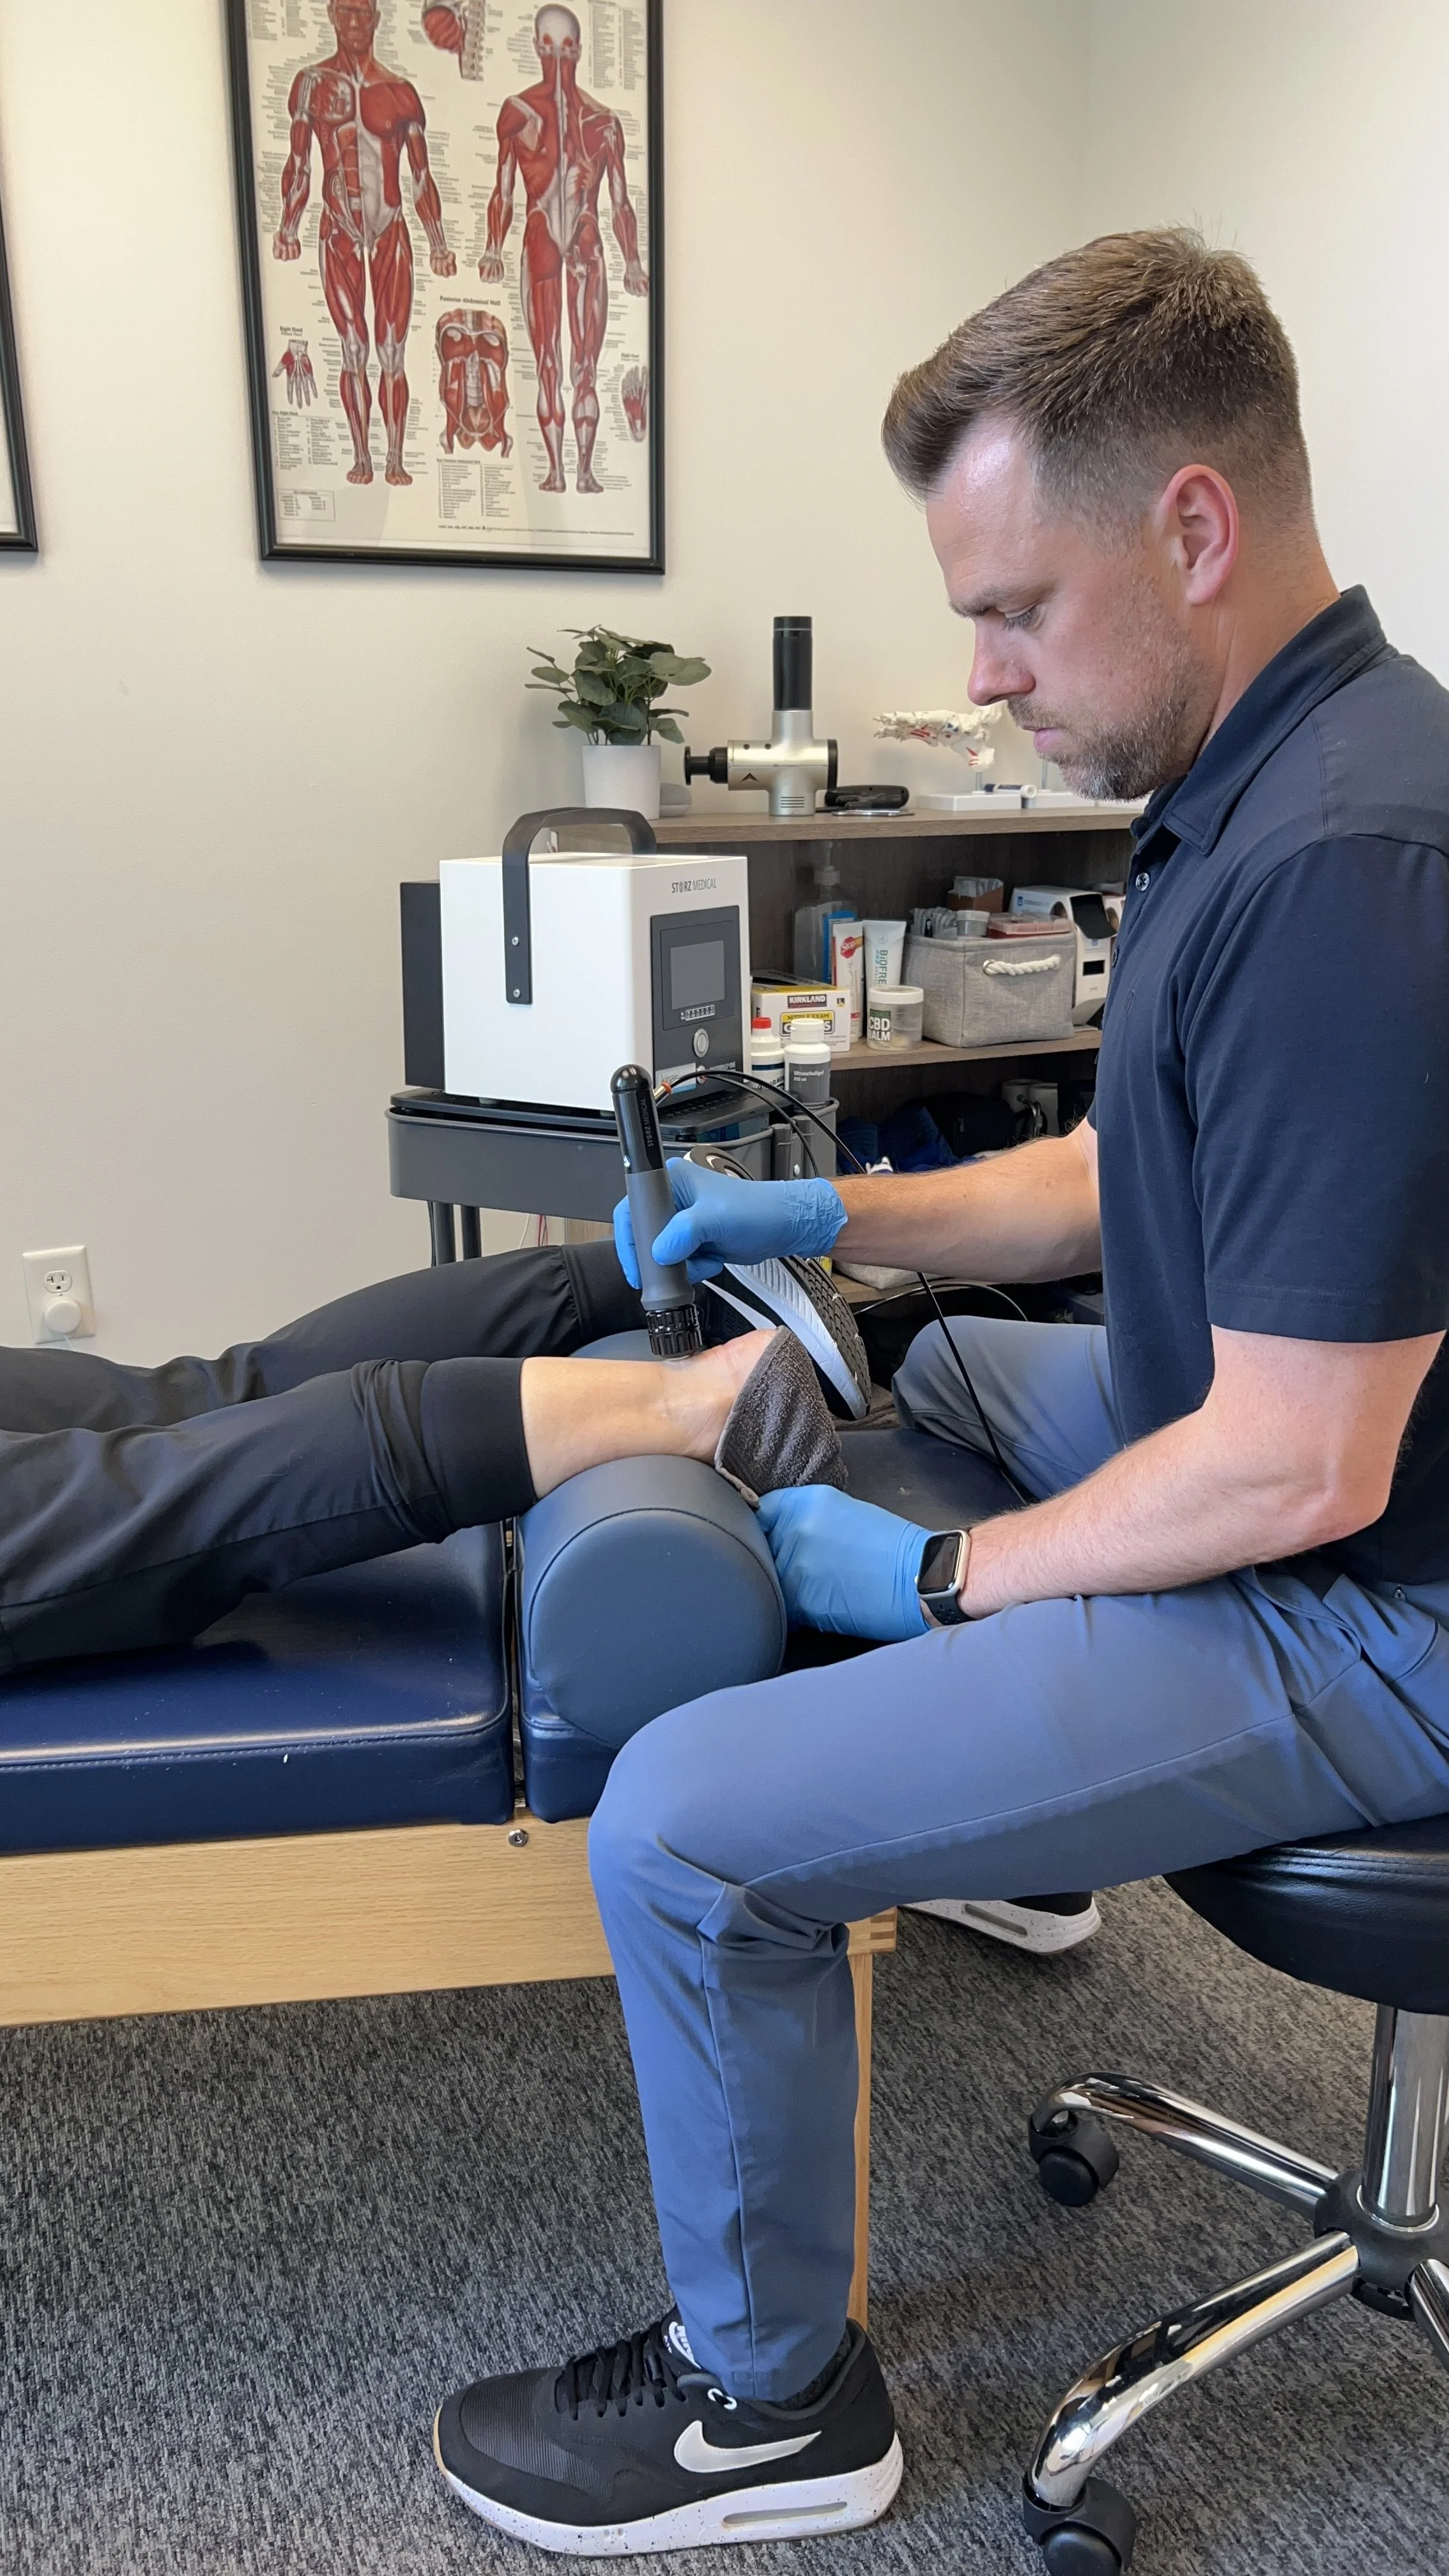
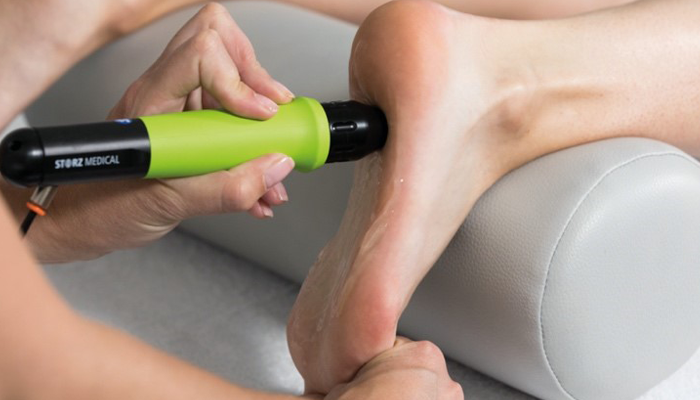
Extracorporeal shockwave therapy (ESWT) delivers focused acoustic pressure waves to the tissues around the knee. It is thought to work by stimulating local blood flow, modulating pain signaling, and encouraging the body’s tissue-repair responses. It is non-invasive, performed in the office in a few minutes, and requires no medication or downtime.
The research on shockwave for knee OA is genuinely promising. A systematic review and meta-analysis of randomized trials found that ESWT significantly improved pain and function in people with knee osteoarthritis, with an average pain reduction on the VAS scale, meaningful improvements in WOMAC function scores, and better range of motion, all with few minor side effects. 3 The strongest effects were seen in the short to medium term, which fits how we use it: as a way to reduce pain enough that you can engage fully in strengthening and return to activity.
Best Knee OA Treatment: Why We Combine These and Always Add Exercise
Each of these tools can reduce pain and improve movement, but none of them, on their own, rebuilds the strength and capacity an arthritic knee needs for the long haul. That’s why we treat them as a bridge. Soft tissue therapy, joint manipulation, and shockwave therapy calm the joint and restore comfortable motion; exercise rehab then builds the durable strength and control that keep symptoms down and help reduce future flare-ups. International guidelines are clear that active, exercise-based management belongs at the center of knee OA care, with hands-on modalities as valuable supporting players. 5
This combination of treatment modalities to relieve, restore, and rebuild is the backbone of how we approach knee osteoarthritis at Revive Sport & Spine. In Part 4, the final article in this series, we get specific about the exercise rehab that manages the condition long-term and keeps you doing what you love.
Key Takeaways Before We Progress to Part 4
✓ Our in-clinic care targets the painful, sensitized tissues around an arthritic knee to restore comfortable movement.
✓ Adding manual therapy to exercise improves pain and function more than exercise alone for knee OA. 1
✓ Manual therapy for the knee appears clinically effective and safe, though study quality varies, which is why we pair it with exercise. 2
✓ Shockwave therapy can improve pain, function, and range of motion in knee OA in the short term with few side effects. 3
✓ These hands-on tools work best as a bridge into the active rehab plan covered in Part 4.
Ready to get your knee moving with less pain? We’ll assess your knee, explain which of these tools fit your situation, and combine them with a rehab plan built around your goals. Stop waiting for the pain to just ‘go away’; schedule your appointment today
Frequently Asked Questions About Knee Osteoarthritis
Can a chiropractor help with knee osteoarthritis?
Yes. Sports chiropractic care for knee OA typically combines soft tissue therapy, joint manipulation and mobilization, and often shockwave therapy, all paired with exercise rehab. Adding hands-on manual therapy to exercise improves pain and function more than exercise alone. 1
Does shockwave therapy work for knee arthritis?
Evidence from randomized trials shows that extracorporeal shockwave therapy can significantly reduce pain and improve function and range of motion in knee osteoarthritis in the short- to medium-term, with few minor side effects. 3 It works best combined with a strengthening program.
Is joint manipulation safe for an arthritic knee?
Manual therapy, including joint manipulation for the knee, is considered generally safe and clinically effective, especially when combined with exercise. We tailor the techniques to your comfort and stage of osteoarthritis. 1 2
How is soft tissue therapy helpful if the problem is the joint?
An arthritic knee is guarded by tight, tender muscles and connective tissue that increase pain and alter how the joint loads. Soft tissue therapy reduces that guarding and sensitivity, making movement and strengthening more comfortable. 4
Will these treatments cure my osteoarthritis?
No treatment reverses established osteoarthritis, but this combination can substantially reduce pain, improve function, and, alongside exercise, help you manage the condition and prevent flare-ups long term. 5
REFERENCES
1. Anwer S, et al. The Benefits of Adding Manual Therapy to Exercise Therapy for Improving Pain and Function in Patients With Knee or Hip Osteoarthritis: A Systematic Review With Meta-analysis. JOSPT. 2022. https://www.jospt.org/doi/10.2519/jospt.2022.11062
2. Feng Q, et al. Effectiveness and safety of manual therapy for knee osteoarthritis: An overview of systematic reviews and meta-analyses. Frontiers in Public Health. 2023;11:1081238. https://www.frontiersin.org/journals/public-health/articles/10.3389/fpubh.2023.1081238/full
3. Avendaño-Coy J, et al. Extracorporeal shockwave therapy improves pain and function in subjects with knee osteoarthritis: A systematic review and meta-analysis of randomized clinical trials. International Journal of Surgery. 2020;82:64-75. https://pubmed.ncbi.nlm.nih.gov/32798759/
4. Xu Y, et al. The Efficacy of Manual Therapy in Patients with Knee Osteoarthritis: A Systematic Review. Medicina (Kaunas). 2021;57(7):696. https://pmc.ncbi.nlm.nih.gov/articles/PMC8304320/
5. Bannuru RR, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. 2019;27(11):1578-1589. https://pubmed.ncbi.nlm.nih.gov/31278997/

Knee Osteoarthritis: Risk Factors, Prevention, Nutrition, and When to Seek Care
Knee osteoarthritis is one of the most common reasons people walk into our sports chiropractic office in Murray, and it is also one of the most misunderstood. In Part 1, we described knee osteoarthritis (OA) as a whole-joint condition driven by a mismatch between joint load and its capacity to handle it. That framing is useful because it points directly to what you can influence. This article covers the factors that raise your risk, the strategies that genuinely help with prevention, what the nutrition research does and doesn’t support, and the signs that mean it’s time to have your knee looked at.
What Raises Your Risk of Knee Osteoarthritis?
Some risk factors are outside your control. Age increases risk; women are affected more often than men; genetics play a role; and a previous significant knee injury, such as an ACL tear, meniscus damage, or fracture, raises the odds of developing OA in that joint years later. Joint alignment and anatomy matter too.
The good news is that several of the most powerful risk factors are modifiable. Body weight is at the top of that list. Excess weight increases the mechanical load through the knee with every step, but it also contributes through metabolic and inflammatory pathways, which is why obesity is linked to OA even in non-weight-bearing joints. Research consistently shows that higher body weight is associated with both a greater risk of developing knee OA and more severe pain and functional limitation once it is present. 1 6 Other modifiable contributors include weak or deconditioned muscles around the knee and hip, occupations or activities involving heavy repetitive loading, and poorly managed prior injuries.
A Quick Anatomy Review
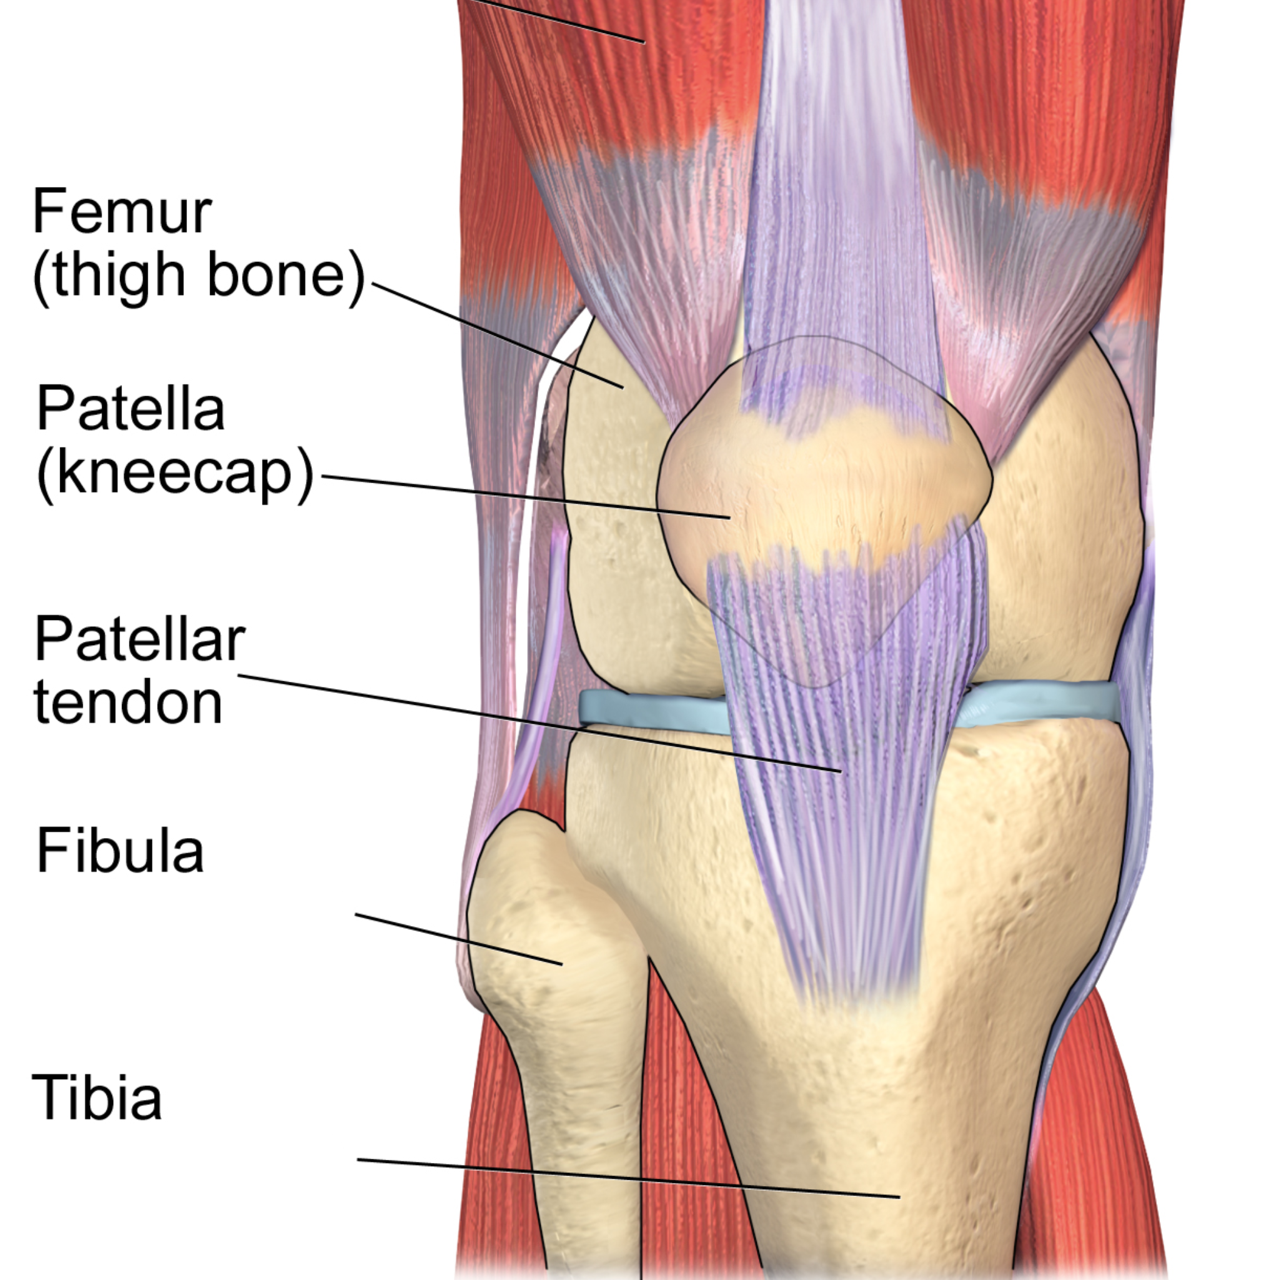
Between the femur and tibia sit two C-shaped shock absorbers called the menisci. They spread the load across the joint, add stability, and protect the cartilage underneath. Surrounding the whole joint is a capsule lined with synovium, a thin membrane that produces synovial fluid to lubricate and nourish the cartilage. Ligaments such as the ACL, PCL, LCL, and MCL hold the bones in alignment, while the muscles that cross the knee, especially the quadriceps and hamstrings, control movement and absorb force. Just beneath the cartilage lies the subchondral bone, which plays a bigger role in osteoarthritis than most people realize.
What Actually Helps to Prevent Osteoarthritis (or slows it down)
Because weight is such a strong and modifiable driver, weight management is one of the highest-yield prevention strategies available. A meta-analysis of observational studies estimated that preventing obesity could meaningfully reduce the incidence of knee osteoarthritis at the population level by almost 30. 2 For someone already carrying extra weight, even modest weight loss reduces knee load and symptoms.
Staying active is the second pillar. Contrary to the old fear that exercise “wears out” the knees, regular moderate activity and strong supporting muscles protect the joint by improving its capacity to absorb load. Keeping the quadriceps, hamstrings, and hip muscles strong, maintaining good range of motion, and addressing prior injuries properly all help keep the load-to-capacity balance in your favor. We will cover the specifics of exercise in Part 4 of this series.
How Can Your Nutrition Affect Your Risk of Osteoarthritis?
Patients often ask which foods or supplements will fix their knees. It’s worth being honest here: no diet or supplement reverses established osteoarthritis, and the marketing around joint supplements far outpaces the evidence. That said, nutrition is not irrelevant. 3
The strongest dietary evidence supports an overall healthy, anti-inflammatory eating pattern. Something similar to a Mediterranean-style diet rich in vegetables, fruit, whole grains, fish, and healthy fats, and lower in ultra-processed foods and added sugar. Long-chain omega-3 fatty acids (from oily fish) and adequate vitamin D are frequently discussed, and correcting a genuine deficiency is reasonable, but evidence that isolated supplementation alters the disease course is limited. 3 4 Popular products like glucosamine and chondroitin have mixed reviews, with some patients having good relief with consistent use, but major studies and guidelines do not strongly recommend them. 5
The practical takeaway: use nutrition to manage weight and support overall health rather than chasing a single “joint miracle” supplement. If you’re considering supplements, it’s worth discussing them with your healthcare team to find the best options for your particular concerns.
When Should You Seek Care for Your Knee Pain?
Knee pain is easy to dismiss, but certain signs mean you shouldn’t wait. Consider getting your knee evaluated if you have pain that persists for more than a few weeks, pain that limits walking, climbing stairs, work, or sleep, ongoing swelling, a knee that locks, catches, or gives way, or stiffness that consistently lingers after rest.
NOTE: Rapidly worsening pain, a hot and visibly swollen joint, fever, or an inability to bear weight warrants prompt medical attention, as those can signal something other than routine osteoarthritis.
Seeking care early has a real advantage: the sooner you address strength, movement, and load, the more you can do to keep the joint functioning well and avoid the deconditioning spiral described in Part 1. Guidelines recommend starting with conservative, active management rather than jumping to imaging or surgery for most people. 5
In Part 3, we’ll walk through exactly how we care for knee osteoarthritis at Revive Sport & Spine, including soft-tissue therapy, joint manipulation, and shockwave therapy, and how these approaches set the stage for the rehab exercise plan in Part 4.
Key Takeaways Before We Progress to Part 3
✓ Excess body weight through diet and exercise is one of the strongest and most modifiable risk factors for knee osteoarthritis. 1 2
✓ No supplement “cures” OA, but weight management and an overall healthy, anti-inflammatory dietary pattern have the best evidence. 3 4
✓ Persistent swelling, locking, giving way, or pain that limits daily life are signals to get your knee evaluated. 5
If your knee has been nagging or you have risk factors and want to stay ahead of osteoarthritic changes and pain, an assessment is a smart first step. We’ll assess your movement, strength, and daily load and help you develop a realistic prevention or management plan.
Frequently Asked Questions
What is the biggest risk factor for knee osteoarthritis?
Excess body weight is among the strongest and most modifiable risk factors. It increases mechanical load on the knee, drives inflammation, and is linked to both developing OA and worse symptoms. 1 2 6
Can knee osteoarthritis be prevented?
You can’t change age or genetics, but you can lower your risk by maintaining a healthy weight, staying active, keeping the muscles around the knee strong, and properly rehabilitating any knee injuries. Preventing obesity alone could reduce up to 30% of knee OA cases. 2
What is the best diet for knee osteoarthritis?
There is no magic food, but the best-supported approach is using nutrition to reach and maintain a healthy weight alongside an overall anti-inflammatory, Mediterranean-style pattern rich in vegetables, fish, and healthy fats. 3 4
Do glucosamine and chondroitin work for knee arthritis?
While some patients swear by it, high-quality trials show inconsistent results, and major clinical guidelines do not strongly recommend them. They are generally safe, but they should not replace weight management, exercise, a reasonable diet, and appropriate care. 5
When should I see someone about knee pain?
Get evaluated if pain lasts more than a few weeks, limits daily activities, or is accompanied by swelling, locking, or giving way. A hot, swollen joint with fever or an inability to bear weight needs prompt emergency medical attention. 5
REFRENCES
1. Batushansky A, et al. Obesity-Related Knee Osteoarthritis — Current Concepts. (Review). 2023. https://pmc.ncbi.nlm.nih.gov/articles/PMC10456094/
2. Zheng H, Chen C. What if we prevent obesity? Risk reduction in knee osteoarthritis estimated through a meta-analysis of observational studies. Arthritis Care & Research. 2011. https://pubmed.ncbi.nlm.nih.gov/21425246/
3. Diet in Knee Osteoarthritis — Myths and Facts. Nutrients. 2025;17(11):1872. https://www.mdpi.com/2072-6643/17/11/1872
4. Thomas S, et al. What is the evidence for a role for diet and nutrition in osteoarthritis? Rheumatology. 2018;57(suppl_4):iv61-iv74. https://academic.oup.com/rheumatology/article/57/suppl_4/iv61/4975692
5. Bannuru RR, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. 2019;27(11):1578-1589. https://pubmed.ncbi.nlm.nih.gov/31278997/
6. Onishi K, et al. Level of obesity is directly associated with the clinical and functional consequences of knee osteoarthritis. Scientific Reports. 2020;10:3601. https://www.nature.com/articles/s41598-020-60587-1

Understanding Knee Osteoarthritis: The Anatomy and How It Actually Develops
Knee osteoarthritis is one of the most common reasons people walk into our sports chiropractic office in Murray, and it is also one of the most misunderstood. Most patients arrive believing their knee is simply “worn out” and that nothing can be done but wait for a replacement. The reality is more hopeful and more interesting. To make good decisions about your knee, it helps to understand what the joint is made of and what is actually happening inside it when osteoarthritis develops. That is the goal of this first article in our four-part series.
A Quick Tour of the Knee Joint - Involved Anatomy
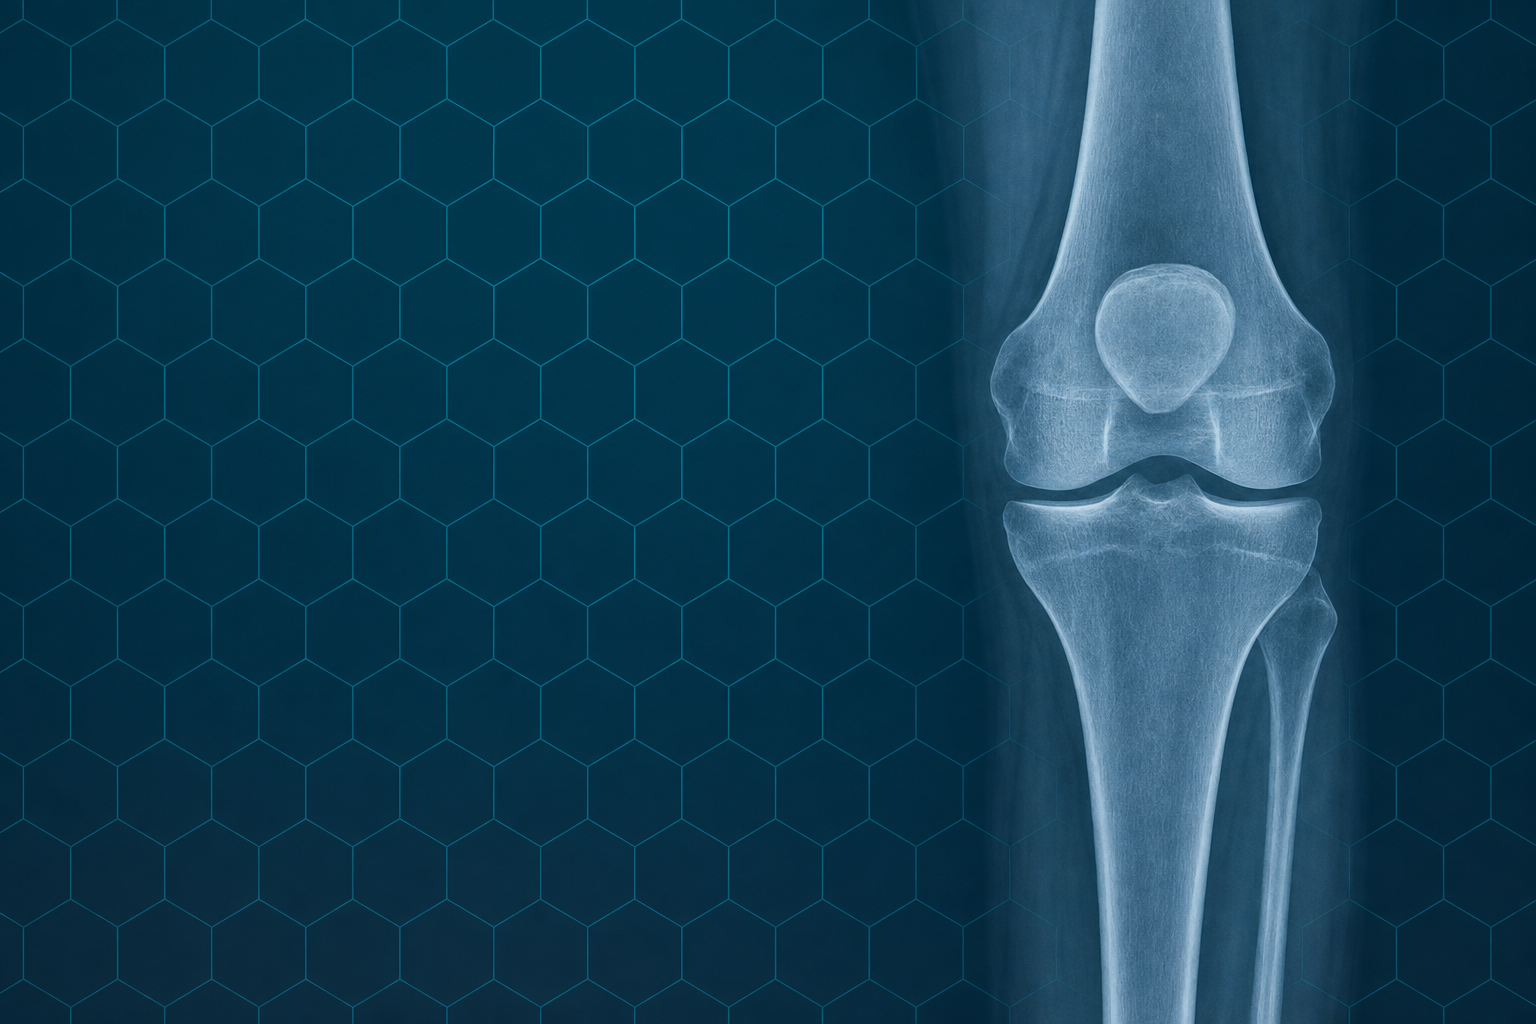
The knee is where three bones meet: the femur (thigh bone), the tibia (shin bone), and the patella (kneecap). Where these bones meet, their ends are capped with articular cartilage, a smooth, slippery, rubbery tissue that is only a few millimeters thick. Healthy cartilage is remarkably low-friction, allowing the bones to glide across one another thousands of times a day without any pain or grinding.
Between the femur and tibia sit two C-shaped shock absorbers called the menisci. They spread load across the joint, add stability, and protect the cartilage underneath. Surrounding the whole joint is a capsule lined with synovium, a thin membrane that produces synovial fluid to lubricate and nourish the cartilage. Ligaments such as the ACL, PCL, LCL, and MCL hold the bones in alignment, while the muscles that cross the knee, especially the quadriceps and hamstrings, control movement and absorb force. Just beneath the cartilage lies the subchondral bone, which plays a bigger role in osteoarthritis than most people realize.
So, What is Osteoarthritis, Really?
For decades, osteoarthritis was described as “wear and tear” of the knee joint, as if the joint were a tire slowly balding. Current research paints a very different picture. OA is now understood as an active disease of the entire joint, not just passive erosion of cartilage. Cartilage, subchondral bone, the synovium, ligaments, and even the surrounding muscles are all involved in the process. 1
In a healthy joint, cartilage is constantly maintained by cells called chondrocytes, which balance the breakdown and rebuilding of the cartilage matrix. In osteoarthritis, that balance tips toward breakdown. Chondrocytes shift into a more inflammatory, catabolic state, releasing enzymes that degrade the cartilage faster than it can be repaired. Low-grade inflammation in the joint lining adds to the problem, and the subchondral bone begins to remodel and stiffen, sometimes forming the bony spurs (osteophytes) seen on X-rays. 1 2
Why the Joint can Hurt, and Why it Sometimes Doesn’t.
Here is a detail that surprises many patients: cartilage itself has no nerve endings and no blood supply. That means early cartilage changes can be completely painless. Pain in osteoarthritis usually arises from other structures, such as the richly innervated subchondral bone, the inflamed synovium, the stretched joint capsule, and the irritated surrounding tissues. 2, 3 This is one reason the amount of change on an X-ray often does not match the amount of pain a person feels. Some people with dramatic imaging have little pain, while others with mild imaging changes experience considerable pain.
What Drives the Knee Osteoarthritic Process Forward?
Osteoarthritis is best understood as an imbalance between the load placed on a joint and that joint’s ability to handle it. Mechanical stress is a key driver: repetitive overload, previous injury, joint malalignment, or weak supporting muscles can all push the joint past what it can comfortably tolerate, triggering the cellular and inflammatory changes described above. 1 Once the cycle starts, pain leads to less movement, less movement leads to weaker muscles and stiffer tissue, and a more poorly supported joint is loaded even less evenly, which can accelerate the degenerative process.
That cycle is exactly why the modern, evidence-based approach to knee OA emphasizes restoring the joint’s capacity through movement, strengthening, and load management rather than simply resting and waiting. International treatment guidelines now list exercise and appropriate physical care as core, first-line strategies for knee osteoarthritis. 4
Key Takeaways Before we Progress to Part 2
Knee osteoarthritis is a whole-joint condition driven by a mismatch between load and capacity, not an inevitable, untreatable breakdown. Because the joint is a living, adaptable system, the way you load it, strengthen it, and care for it genuinely matters. In Part 2, we’ll look at the specific factors that raise your risk, what you can do to help prevent osteoarthritis or slow its progression, the role nutrition plays, and the warning signs that mean it’s time to have your knee evaluated.
✓ The knee is a load-bearing joint where the femur, tibia, and patella glide on a thin layer of articular cartilage cushioned by menisci.
✓ Osteoarthritis (OA) is not simply “wear and tear”; it is an active, whole-joint disease involving cartilage, bone, and the joint lining. 1
✓ Cartilage has no blood supply or nerves, so early OA is often silent until changes reach the bone and surrounding tissues. 2
✓ Understanding the mechanism helps explain why movement, load management, and targeted therapy, not just rest, are central to care. 4
Not sure whether your knee pain is early osteoarthritis or something else? A focused evaluation is the best place to start. Our sports chiropractic team assesses how your knee moves and loads, then builds a plan around your goals, no guesswork, no assuming surgery is inevitable.
Frequently Asked Questions
Is knee osteoarthritis just wear and tear?
No. While mechanical load matters, osteoarthritis is an active disease of the whole joint involving cartilage cells, low-grade inflammation, and changes in the underlying bone, not simply passive erosion. This is why targeted movement and therapy can meaningfully influence how the joint feels and functions. 1
Why does my knee X-ray look bad but not hurt much (or vice versa)?
Cartilage has no nerves, so cartilage loss alone is painless. Pain comes from the bone beneath the cartilage, the joint lining, and surrounding soft tissues, which is why imaging severity and pain levels often don’t match. 2 3
Is there anything that can be done for knee osteoarthritis besides surgery?
Yes. For most people, surgery is not the first step. Evidence-based guidelines recommend exercise, load management, and conservative care such as joint manipulation, dry needling, and shockwave therapy as first-line treatment, and many patients manage their knees well for years without an operation. 4
What structures make up the knee joint?
The knee is formed by the femur, tibia, and patella, capped with articular cartilage and cushioned by two menisci. A synovial lining lubricates the joint, ligaments provide stability, and the quadriceps and hamstrings control and absorb load.
REFERNECES
1. Tong L, et al. Current understanding of osteoarthritis pathogenesis and relevant new approaches. Bone Research. 2022;10:60. https://www.nature.com/articles/s41413-022-00226-9
2. Du X, et al. Research Progress on the Pathogenesis of Knee Osteoarthritis. Orthopaedic Surgery. 2023. https://onlinelibrary.wiley.com/doi/10.1111/os.13809
3. Yao Q, et al. Osteoarthritis: pathogenic signaling pathways and therapeutic targets. Signal Transduction and Targeted Therapy. 2023;8:56. https://www.nature.com/articles/s41392-023-01330-w
4. Bannuru RR, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. 2019;27(11):1578-1589. https://pubmed.ncbi.nlm.nih.gov/31278997/

Iliotibial Band Syndrome: Self-Care & Training Modification
As we work our way through this series, let not forget what we have learned so far.
Iliotibial band syndrome is a common overuse injury plaguing runners of all abilities. The most common offense is trying to increase your volume too soon while also increasing the intensity without cross-training or varying surfaces.
The Iliotibial band DOES NOT STRETCH! The tension we feel is caused by the muscles that support the IT band, Tensor Fascia Latae and Gluteus Maximus.
The stabbing pain we experiences as runners suffering from IT band syndrome is thought to be caused by the band itself shifting forward and backward as the knee flexes and extends. The research is out on that one…if we ever reach a consensus, I will let you all know!
Where are we now? Well…if you have made it this far, you are probably dealing with IT band syndrome and wondering if it will ever go away and let you get back to running the way you would like.
For this, we are going to discuss self-care. What you can do about the knee pain and tight hips at home while also mentioning a few stretches you can do at work or out on a run. Our goal is simple - Allow you to continue to train, modified while improving your IT band syndrome pain week-to-week.
What we are talking about today, where the real work takes place, the day in and day out self-care. And the big question….can you continue training?
As we work our way through this series, let not forget what we have learned so far.
Iliotibial band syndrome is a common overuse injury plaguing runners of all abilities. The most common offense is trying to increase your volume too soon while also increasing the intensity without cross-training or varying surfaces.
The Iliotibial band DOES NOT STRETCH! The tension we feel is caused by the muscles that support the IT band, Tensor Fascia Latae and Gluteus Maximus.
The stabbing pain we experiences as runners suffering from IT band syndrome is thought to be caused by the band itself shifting forward and backward as the knee flexes and extends. The research is out on that one…if we ever reach a consensus, I will let you all know!
Where are we now? Well…if you have made it this far, you are probably dealing with IT band syndrome and wondering if it will ever go away and let you get back to running the way you would like.
For this, we are going to discuss self-care. What you can do about the knee pain and tight hips at home while also mentioning a few stretches you can do at work or out on a run. Our goal is simple - Allow you to continue to train, modified while improving your IT band syndrome pain week-to-week.
What we are talking about today, where the real work takes place, the day in and day out self-care. And the big question….can you continue training?
SELF CARE PART 1 - START WITH A BETTER WARM-UP
I can not stress this enough! As you are working through an injury, maintaining some kind of load (training volume) is important, but you are better served spending time on a proper warm up, running just a few miles, then spending a good amount of time on the cool down. With just about every running injury we deal with, runners have a dismal warm-up if one at all. Most are so pressed for time, they lace up the shoes, run out the door, only to return and head straight to work. Most of us are not teenagers anymore, our bodies just can’t do this…not for long periods anyway. Start with a thorough warm-up - we will emphasize this again in our next article where we talk rehab and return to running so prepare yourself!
SELF CARE PART 2 - SELF MYOFASCIAL RELIEF
Understanding that foam rolling and stretching of the IT band itself is ineffective, where do we focus our attention? The hips…it is always the hips! But some attention at the knee can be beneficial while appropriate rest and recovery are always suggested after an acute flair-up or long run.
Rest & Recovery:
Traditional pain relievers for running related pain include ice, heat, topical creams like biofreeze, and some good old-fashioned rest. Today we have an array of tools that can aid in recovery, one we like to use frequently are compression boots from Rapid Reboot. We don’t expect everyone just to have these lying around, but they sure feel great after some dry needling, IASTM, and manipulation in the clinic.
Rolling & Stretching:
Now that we understand what anatomy we need to address, it is time to get your roll on! If we are able to continue to train, we suggest rolling and stretching 4-5 times each day. Before you lose it, these sessions are only 3-4 minutes each. If you are a frequent runner, or just starting out, here are the basics.
Rollers should be in your home, office, and car. You should have at least 3 lacrosse balls around, purse, cup holder in your car, in your desk, and your gym bag.
Roll in the morning, pre and post run, after your lunch break, when you get home, and then a good session before bed.
Cupping & Flossing:
These may not be tools accessible to all, but they help you achieve stretching in ways that are difficult to do on your own. One of my personal approaches to provide relief to the knee pain we experience with IT Band syndrome is to place a few cups (I have a few sets of these) around the lateral knee and lateral quadricep muscle, walk about for a few minutes, perform a few squats, rinse and repeat 2-3 times per week.


SELF CARE PART 3 - TRAINING MODIFICATION
Training modification is the hardest part to address. For most, the ability to continue training toward your race is almost as important as fixing the injury. While maintaining some load is ideal, there are instances where a total shut-down is necessary for a few weeks. If you are a typical runner, meaning that you are going to run through the injury, we must modify. Here are the basics. Remember that Iliotibial band syndrome is the result of too much mileage or intensity, too soon in your training plan. Not having a proper base as you head into a 20-week marathon training plan is a recipe for disaster.
Our first suggestion is to cut your volume by 50% and decrease your intensity for the next 2-4 weeks. Our goal is to maintain some running, but the speed work and downhill bombs need to take a backseat for a while.
Please, cross-train! As runners, we think that running is it, period. When we are injured, and more so when we are not so that we can prevent injury, we must cross train. If you have been battling IT band syndrome for more than a few weeks, it is time to work in some biking, swimming and weightlifting. This allows you to maintain most of your cardiovascular capacity while taking out the pounding associated with running.
Lastly, look at your running form. Can it be cleaned up a bit? For most of us, that is a very strong, Yes! I’m not saying to go out and get an extensive running evaluation to change the subtle nuances of your stride, most of us just are not at that level, but shortening your stride, increasing your cadence, and working on your running drills can provide a needed boost in your running efficiency.
Cadence should be upwards of 170-180 steps per minute.
Perform drills on a soft surface (track or field) 2-3 times per week.
More on this in the rehab portion next week.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in the Greater Salt Lake City Area of Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Runner's Knee Bonus: Patellofemoral Pain Syndrome - Not Just For Runners
For several weeks we have been covering patellar femoral pain syndrome (PFPS), or runner’s knee as many like to call it. However, as with many of the conditions we see, it can be found in more than just one population of people. PFPS can also be caused by other physical activities that put repeated stress on the knee. This can include squatting, jumping, climbing stairs, etc. Along with that, PFPS can occur when you have patellar malalignment, which was touched on in Part 1 of our Runner’s Knee series.
With most PFPS we see, it comes from a sudden increase of load placed on the knee. So if you have recently increased your weight at the gym, time on the Stairmaster, or taken on a new activity, if the stress level on your knees has increased you could experience “runner’s knee” even if you do not consider yourself a runner. With that said, here are a few preventative measures we can implement that could help.
For several weeks, we have been covering patellofemoral pain syndrome (PFPS), or runner’s knee, as many like to call it. However, as with many of the conditions we see, it can be found in more than one population. PFPS can also be caused by other physical activities that put repeated stress on the knee. This can include squatting, jumping, climbing stairs, etc. Additionally, PFPS can occur with patellar malalignment, as touched on in Part 1 of our Runner’s Knee series.
Most PFPS we see come from a sudden increase in load on the knee. So if you have recently increased your weight at the gym, time on the StairMaster, or taken up a new activity, and the stress on your knees has increased, you could experience “runner’s knee” even if you do not consider yourself a runner. With that said, here are a few preventive measures we can implement to help.
PREVENTIVE TECHNIQUE #1:
If you are squatting, jumping, or having difficulty hiking or climbing stairs, ensure you get a proper warm-up. In addition to the treatment options listed in Part 3 of our Runner’s Knee series, you can perform band exercises before your activity. Each of these exercises is
beneficial in increasing our mobility and strength, as well as providing our bodies with proper preparation for the activities we engage in.
PREVENTIVE TECHNIQUE #2:
An additional preventive measure is to always use proper form. In all things we do, improper form can cause extra strain on our bodies. In all activities, especially lifting and squatting it is important that before we increase weight we ensure that our form is correct. Squatting with our knees in line with our toes, and our back naturally arched allows the weight to be properly distributed throughout, rather than having all the pressure on our knees.
PREVENTIVE TECHNIQUE #3:
The last preventive measure is simple but effective. It is important that we increase our training gradually and not all at once. If you are a lifter, gradually increase weight. If you are a hiker or climb stairs, increase your distance and pace gradually. Our bodies are adaptable, and with steady increase, it can adjust accordingly.
FINDING ANSWERS
So for those of us who are experiencing knee pain in the front of our knees and are not runners, there are answers here for us as well. It just so happens that those answers are very similar to those who run many miles a day. So don’t be afraid to dive into our multi-part series about runner’s knee. I think you will be able to find answers to your knee pain as well.
Check out the Part 1, Part 2, Part 3, and Part 4 of our Patellofemoral pain syndrome series here.
Janaye Freeman is a Certified Athletic Trainer & Lead Therapy Technician at Revive Sport & Spine in Murray, Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management for Murray, Holladay, Cottonwood Heights, Millcreek, Midvale, and Sandy.