THOUGHTS ON:
Training, Rehabilitation,
&
Best Care Practices

Medial Tibial Stress Syndrome Part 2 - Self-Care For Shin Splints
In PART 1 of our Shin Splints series, we took a look at the anatomy associated with medial tibial stress syndrome as well as the factors that make runners especially susceptible to them, namely the repetitive nature of running compounded by most cases typically doing too much too soon. Here in PART 2, we are going to look at self-care options as well as some considerations for preventing repeate episodes of shin splints so that you can keep running and training for your goal races.
In PART 1 of our Shin Splints series, we took a look at the anatomy associated with medial tibial stress syndrome as well as the factors that make runners especially susceptible to them, namely the repetitive nature of running compounded by most cases typically doing too much too soon.
Here in PART 2, we are going to look at self-care options as well as some considerations for preventing repeate episodes of shin splints so that you can keep running and training for your goal races.
SELF CARE OPTIONS FOR MTSS-SHIN SPLINTS
Self Myofacial Release - 4 Ways To Care For Your Shin Splint Pain
Pre-Running Warm-Up For Shin Splints
Training Modifications, Gear Suggestions, & Other Prevention Considerations
Form, Cadence, & Ground Contact Time:
This is a tricky subject, honestly I’m not sure why I even mentioned it. One can go miles down the form training rabbit hole and come out the other side worse they they were before. However, I do want to mention three things that must be considered and worked into your training plan to help prevent shin splints and make you a more efficient and faster runner.
The ground fights back! The more time we spend in contact with the ground, the harder this battle will be. I’m not here to talk about heel-striking, forefoot running, etc., but I will mention cadence. The higher your cadence, the less time your foot spends on the ground. Meaning, the less ground reactive forces you absorb and the less stress on your body.
Again, I’m not here to correct form. But I do believe we can all be more efficient. Strength training helps us become more efficient for those later stages of the race. Please add strength training to your program, it is extremely useful.
Alter your surfaces. Don’t always pound the pavement. The track and trails are your friend…and your feet will thank you for it.
Shoes:
Shoes are something I get asked about frequently. My honest answer is this, ‘We have more shoe technology and selection than ever…we also have more injuries than ever.’ Take that for what it is worth but I do believe shoes should be rotated and changed frequently. I suggest a 2-3 pair rotation, avoid running in the same pair two days in a row, and switching out for a new pair every 200-300 miles depending on the shoe.
Warm-Up & Cool-Down:
This is SO BIG. In every injury we encounter and talk about, how you warm-up (if at all) and cool-down has a direct impact on your injury risk, and recovery speed from injury. Warming up prepares your body for the task ahead, giving it the best chance to avoid injury. Colling down helps work out those tight spots after training while encouraging faster recovery.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

New Year - New Goals: Running To Better Health
Improved health tops nearly every new year's resolution list ever made, 2019 will be no different. From this, running comes to the forefront of our ‘get in shape’ plan because of its ease (almost everyone can shuffle one foot in front of the other, not saying it is easy) and relatively low cost (a decent pair of shoes and some running gear is all you need). While this plan seems fool-proof, there is a reason 60%+ of the people we see in our clinic are runners, new and old.
Improved health tops nearly every new year's resolution list ever made, 2019 will be no different. From this, running comes to the forefront of our ‘get in shape’ plan because of its ease (almost everyone can shuffle one foot in front of the other, not saying it is easy) and relatively low cost (a decent pair of shoes and some running gear is all you need). While this plan seems fool-proof, there is a reason 60%+ of the people we see in our clinic are runners, new and old.

While running seems easy to do, there are many things to consider. Are you a runner? Have you ran since high school, or ever? Did you know your body type matters? Can you cover 1-2 miles and not be in misery the next day? Do you have good shoes? Do you have a partner to run with, accountability is essential for follow-through? You didn’t think about any of that, did you? While we will have more running and running-related injury articles to share with you in 2019, let’s start with some current research (Nerd-Alert).
Who:
In this study, the authors gave 914 novice runners a GPS watch and tracked them over a year to study their habits and direction of their running habits. The group was divided into 3 groups based on their BMI (Normal, Overweight, & Obese) to help determine if there were any differences and similarities in their training selection.
What They Found:
The first interesting finding was that in this self-guided exercise program, all categories selected similar training doses. The authors suggest that this may explain the higher injury risk among overweight and obese runners compared with normal-weight runners.
Normal weight runners ran faster and farther than their overweight and obese counterparts. This is anticipated as these are all novice runners, but the perceived effort was not established and could be an interesting metric to develop.
Suggestions:
Starting a new exercise program is exciting, but one must also be willing to understand and see that they are at a starting point. Novice runners are at high risk of injury if they start too fast, or do too much too soon. An initial dose of high volume can lead to an injury that causes you to become inactive, losing any benefits you sought to gain in the first place.
BMI is important to consider. Have a higher BMI does not mean you can or should not run, it means that the programming must be different. Training has to do with ‘load,’ and by that, we mean that if you are 200 lbs, it is a bit more challenging and harder on your body to run 3 miles than for someone who is 150 lbs. This changes as we continue training and adapt, but at first, we must take things slow.
Any activity is better than a sedentary lifestyle! Remember to take things slowly. Your body will be sore, but that is to be expected. If you have pain, or your soreness lasts longer than a few days after exercise, seek professional guidance on preparing your body and running programming.
Who:
The authors of this study followed 447 runners over a 24-week running program. Their goal was to determine the risk associated with high-intensity running plans and high-volume running plans.
Before the study began, they hypothesized that runners on the high-intensity program would have higher rates of Achilles tendinopathy, calf injuries, and plantar fasciitis while runners on the high-volume program would experience more runners knee, iliotibial band syndrome, and patellar tendinopathy.
What they found:
Over the 24-week training program, 80 runners sustained an injury. However, the authors found no difference in the risk of injuries related to training volume or intensity.
Suggestions:
The others suggest this discrepancy between these results and other related studies and running-related injury beliefs are related to the periodization of the running schedules, the scheduled running intensities, and the categorizations of injuries.
Runners or all shape, sizes, and abilities will eventually run into injury. Prevention by adhering to a solid warm-up routine, frequent attention to weaknesses and immobilities, while also modifying a training plan to one's abilities can help prevent injury.
When beginning a new running plan, or increasing your volume or intensity, it is suggested to do one at a time. Listen to your body and take time off as needed.
If you are taking up running again, or for the first time, and you have questions, we are here to help. Running injuries are common. You often do not have to stop running, just a rework and refocus of your training plan. Train Hard & Train Smart.
Happy & Healthy 2019!
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Iliotibial Band Syndrome: Self-Care & Training Modification
As we work our way through this series, let not forget what we have learned so far.
Iliotibial band syndrome is a common overuse injury plaguing runners of all abilities. The most common offense is trying to increase your volume too soon while also increasing the intensity without cross-training or varying surfaces.
The Iliotibial band DOES NOT STRETCH! The tension we feel is caused by the muscles that support the IT band, Tensor Fascia Latae and Gluteus Maximus.
The stabbing pain we experiences as runners suffering from IT band syndrome is thought to be caused by the band itself shifting forward and backward as the knee flexes and extends. The research is out on that one…if we ever reach a consensus, I will let you all know!
Where are we now? Well…if you have made it this far, you are probably dealing with IT band syndrome and wondering if it will ever go away and let you get back to running the way you would like.
For this, we are going to discuss self-care. What you can do about the knee pain and tight hips at home while also mentioning a few stretches you can do at work or out on a run. Our goal is simple - Allow you to continue to train, modified while improving your IT band syndrome pain week-to-week.
What we are talking about today, where the real work takes place, the day in and day out self-care. And the big question….can you continue training?
As we work our way through this series, let not forget what we have learned so far.
Iliotibial band syndrome is a common overuse injury plaguing runners of all abilities. The most common offense is trying to increase your volume too soon while also increasing the intensity without cross-training or varying surfaces.
The Iliotibial band DOES NOT STRETCH! The tension we feel is caused by the muscles that support the IT band, Tensor Fascia Latae and Gluteus Maximus.
The stabbing pain we experiences as runners suffering from IT band syndrome is thought to be caused by the band itself shifting forward and backward as the knee flexes and extends. The research is out on that one…if we ever reach a consensus, I will let you all know!
Where are we now? Well…if you have made it this far, you are probably dealing with IT band syndrome and wondering if it will ever go away and let you get back to running the way you would like.
For this, we are going to discuss self-care. What you can do about the knee pain and tight hips at home while also mentioning a few stretches you can do at work or out on a run. Our goal is simple - Allow you to continue to train, modified while improving your IT band syndrome pain week-to-week.
What we are talking about today, where the real work takes place, the day in and day out self-care. And the big question….can you continue training?
SELF CARE PART 1 - START WITH A BETTER WARM-UP
I can not stress this enough! As you are working through an injury, maintaining some kind of load (training volume) is important, but you are better served spending time on a proper warm up, running just a few miles, then spending a good amount of time on the cool down. With just about every running injury we deal with, runners have a dismal warm-up if one at all. Most are so pressed for time, they lace up the shoes, run out the door, only to return and head straight to work. Most of us are not teenagers anymore, our bodies just can’t do this…not for long periods anyway. Start with a thorough warm-up - we will emphasize this again in our next article where we talk rehab and return to running so prepare yourself!
SELF CARE PART 2 - SELF MYOFASCIAL RELIEF
Understanding that foam rolling and stretching of the IT band itself is ineffective, where do we focus our attention? The hips…it is always the hips! But some attention at the knee can be beneficial while appropriate rest and recovery are always suggested after an acute flair-up or long run.
Rest & Recovery:
Traditional pain relievers for running related pain include ice, heat, topical creams like biofreeze, and some good old-fashioned rest. Today we have an array of tools that can aid in recovery, one we like to use frequently are compression boots from Rapid Reboot. We don’t expect everyone just to have these lying around, but they sure feel great after some dry needling, IASTM, and manipulation in the clinic.
Rolling & Stretching:
Now that we understand what anatomy we need to address, it is time to get your roll on! If we are able to continue to train, we suggest rolling and stretching 4-5 times each day. Before you lose it, these sessions are only 3-4 minutes each. If you are a frequent runner, or just starting out, here are the basics.
Rollers should be in your home, office, and car. You should have at least 3 lacrosse balls around, purse, cup holder in your car, in your desk, and your gym bag.
Roll in the morning, pre and post run, after your lunch break, when you get home, and then a good session before bed.
Cupping & Flossing:
These may not be tools accessible to all, but they help you achieve stretching in ways that are difficult to do on your own. One of my personal approaches to provide relief to the knee pain we experience with IT Band syndrome is to place a few cups (I have a few sets of these) around the lateral knee and lateral quadricep muscle, walk about for a few minutes, perform a few squats, rinse and repeat 2-3 times per week.


SELF CARE PART 3 - TRAINING MODIFICATION
Training modification is the hardest part to address. For most, the ability to continue training toward your race is almost as important as fixing the injury. While maintaining some load is ideal, there are instances where a total shut-down is necessary for a few weeks. If you are a typical runner, meaning that you are going to run through the injury, we must modify. Here are the basics. Remember that Iliotibial band syndrome is the result of too much mileage or intensity, too soon in your training plan. Not having a proper base as you head into a 20-week marathon training plan is a recipe for disaster.
Our first suggestion is to cut your volume by 50% and decrease your intensity for the next 2-4 weeks. Our goal is to maintain some running, but the speed work and downhill bombs need to take a backseat for a while.
Please, cross-train! As runners, we think that running is it, period. When we are injured, and more so when we are not so that we can prevent injury, we must cross train. If you have been battling IT band syndrome for more than a few weeks, it is time to work in some biking, swimming and weightlifting. This allows you to maintain most of your cardiovascular capacity while taking out the pounding associated with running.
Lastly, look at your running form. Can it be cleaned up a bit? For most of us, that is a very strong, Yes! I’m not saying to go out and get an extensive running evaluation to change the subtle nuances of your stride, most of us just are not at that level, but shortening your stride, increasing your cadence, and working on your running drills can provide a needed boost in your running efficiency.
Cadence should be upwards of 170-180 steps per minute.
Perform drills on a soft surface (track or field) 2-3 times per week.
More on this in the rehab portion next week.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in the Greater Salt Lake City Area of Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Iliotibial Band Syndrome: Why Runners? Understanding Biomechanics & Common Risk Factors.
Knowing more about the anatomy associated with the Iliotibial band (IT Band Article #1) is a great start, but that alone will not decrease the stabbing feeling you had on the outside of your knee as you attempted a long run this past weekend.
We are moving forward with our IT Band Syndrome Relief series. This time we aim at the biomechanics (boring for some, but very important) of the Iliotibial band and why it is causing you pain. From there, we are going to look at some common risk factors and other things you are doing every time you go out to run that is making it worse.
Knowing more about the anatomy associated with the Iliotibial band (IT Band Article #1) is a great start, but that alone will not decrease the stabbing feeling you had on the outside of your knee as you attempted a long run this past weekend.

We are moving forward with our IT Band Syndrome Relief series. This time we aim at the biomechanics (boring for some, but very important) of the Iliotibial band and why it is causing you pain. From there, we are going to look at some common risk factors and other things you are doing every time you go out to run that is making it worse.
BASIC BIOMECHANICS
When we look at the function of the Iliotibial Band, it primarily assumes the role of lateral knee stability. Understanding that it originates from the Iliac crest and inserts on the tibia (Gerdy’s tubercle, remember?) we realize that it is a two joint muscle. When a muscle crosses and acts on two joints, in this case, the hip and knee, the likelihood of injury dramatically increases, especially when it is subjected to overuse overload.
With this setup, the IT Band also acts to extend, abduct (raise the leg out to the side), and externally rotate out the hip. As we will discuss in our next article about self-care for the IT Band, we know the muscle of the hip are the primary culprit and where we will focus our attention during clinical and home care.
BUT WHY THE PAIN AT THE KNEE?
While the Iliotibial band crosses the knee to attach to the tibia (fibular and patella according to some studies) providing stability to the outside of the knee, it moves as the knee bends and extends during walking and running.

When we bend our leg, the IT Band moves anterior to, or forward, across the lateral condyle of the femur bone (SNAP!), then, when the knee nears 30 degrees of bend, it moves posteriorly, or back over the lateral condyle of the femur (SNAP!).
Now, think about how many steps you take on your average 5-mile run. If you have tightness in the hip musculature, namely the TFL and Glute Max muscles, they are pulling tension through the IT Band causing an up close and personal relationship between the band and the femoral condyle we just mentioned. When we work through the running gate cycle, we cross the 30 degrees of flexion and extend back out of it over and over….SNAP, SNAP, SNAP!
Take this friction, and add force. The force from each and every foot slap on the ground while running has to be dispersed through the muscles, ligaments, tendons, and joints. While not proven, my own personal ‘journey’ with IT Band Syndrome led me to find that when I trained on softer surfaces, my knee pain was less severe.
Either way, this force, friction, and the magic number of 30 degrees do not play well together. As you can see in this video, if you run with somewhat decent form, your foot strikes the ground somewhere between 20 and 30 degrees of knee flexion (SNAP!) and when you follow-through the gait cycle to push off and bring your leg forward, you near full extension (SNAP!) and back into bending of the knee (SNAP!).
COMMON RISK FACTORS & RUNNING MISTAKES
Common Risk Factor #1: Too Much, Too Hard, Too Soon
We have all done it…try to pick up where we left off either from an injury, vacation, or some much needed time off after a goal race. However, this typically affects the newer runner. You find a plan online, it looks fun, doable, but you soon find out it was too much. Increasing your intensity and volume at the same time spells disaster for the most veteran runner, for the newbies, this is the quickest way to stop running. Take it slow, slower than you want to. Build up your volume, EARN YOUR BASE, then maintain that volume and slowly increase your intensity. THERE IS NO OTHER WAY!
Common Risk Factor #2: Not Taking The ‘Road’ Less Traveled
Do you always run on the road? I mean ALWAYS? How about sticking to one side of the road on every run? We all know that roads are banked, but if you are always running on the right side, your body will adapt to that slight lean, causing problems down the road (pun intended there). With that, try the track, trails, aqua jogging, a treadmill. Just like shoes, you need variety. Note: Watch the video above, and look for pt 3, we talk on this more.
Common Risk Factor #3: “What Is Strength Training?” -Runners Everywhere
One of the most common causes of IT Band Syndrome is weakened hip muscles. It will come as no surprise when we discuss clinical and home care that strengthening the hips is a GIANT part of the rehab and future prevention process. It’s okay runners, I was scared of the weights at one point in time too!
Common Risk Factor #4: Who Has Time To Warm-Up?
The next significant change we make during care is the Warm-Up. If you just said, “The What?” Then we just found the cause of your IT Band Syndrome Pain. Warming up not only helps prevent injury, but it makes you a better runner. There, I said it, now start doing it.
Common Cause #5: Developmental & Gait Abnormalities
Overpronation, leg length discrepancies, bow-leggedness, poor hip mobility due to underlying causes. These are all challenging, and for most, they just add to the problem. A perfect example is that I personally found that I have a 1.5 cm short leg. I found this out when I was over 30, my body was adapted to it. Putting a lift in or selecting a supportive shoe would have only worsened my condition. I did, however, have to be strategic in my strength training, mobility work, and where and how I trained. If you fall into this category, call our office, or someone near you that understands running injuries as you do need help from a professional to find the right rehab exercise and mobility drills to help you run pain-free.
SUMMARY
Tight and weak hips lead to poor function and support of the IT Band. This allows the band to SNAP at the knee, producing overuse friction, and long-standing pain.
Risks come in all varieties, some you are doing every day. Take your training slow, work in strength training, vary your training surfaces, and warm up before running!
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in the Greater Salt Lake City Area of Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Iliotibial Band Syndrome: Anatomy & Symptoms Of The Most Common Running Injury
You are out on another long run. It is a mid-Saturday morning, the weather is a cool 50 degrees, clear skies, and your focus is on the audiobook or podcast playing through your headphones. All of a sudden, out of nowhere, you get this sharp, STABBING, pain on the outside of your knee. Where did this come from? Did you do something wrong? What the heck is happening?
If this is your first time dealing with Iliotibial band syndrome, or you are remembering your first experience with it right now, the feeling is all too real. IT Band issues are a frequent occurrence for runners of all abilities, one of the most common conditions we relieve in our office and feel so prevalent that it is almost a ‘right of passage’ of sorts for new runners.
You are out on another long run. It is a mid-Saturday morning, the weather is a cool 50 degrees, clear skies, and your focus is on the audiobook or podcast playing through your headphones. All of a sudden, out of nowhere, you get this sharp, STABBING, pain on the outside of your knee. Where did this come from? Did you do something wrong? What the heck is happening?

If this is your first time dealing with Iliotibial band syndrome, or you are remembering your first experience with it right now, the feeling is all too real. IT Band issues are a frequent occurrence for runners of all abilities, one of the most common conditions we relieve in our office and feel so prevalent that it is almost a ‘right of passage’ of sorts for new runners.
In this series, we are going to dive into the details of IT band issues, what causes this dreaded running injury, what you can do about it when it happens to you (It Will!), and when you need to seek care to help get your training back on track. I can tell you from experience, as a past sufferer of IT band issues myself, it can be stubborn, frustrating, and damaging to your confidence as a runner…but it does not have to be.
I tell patients daily that IT Band syndrome is a relatively easy condition to treat…but it requires time, effort, and a change of routine. We start here today by understanding what it is and move through this series to self-treatment and prevention.
WHAT MAKES UP THE IT BAND…
… and why you can’t just stretch the Iliotibial band and make it better.
IMPORTANT ANATOMY:
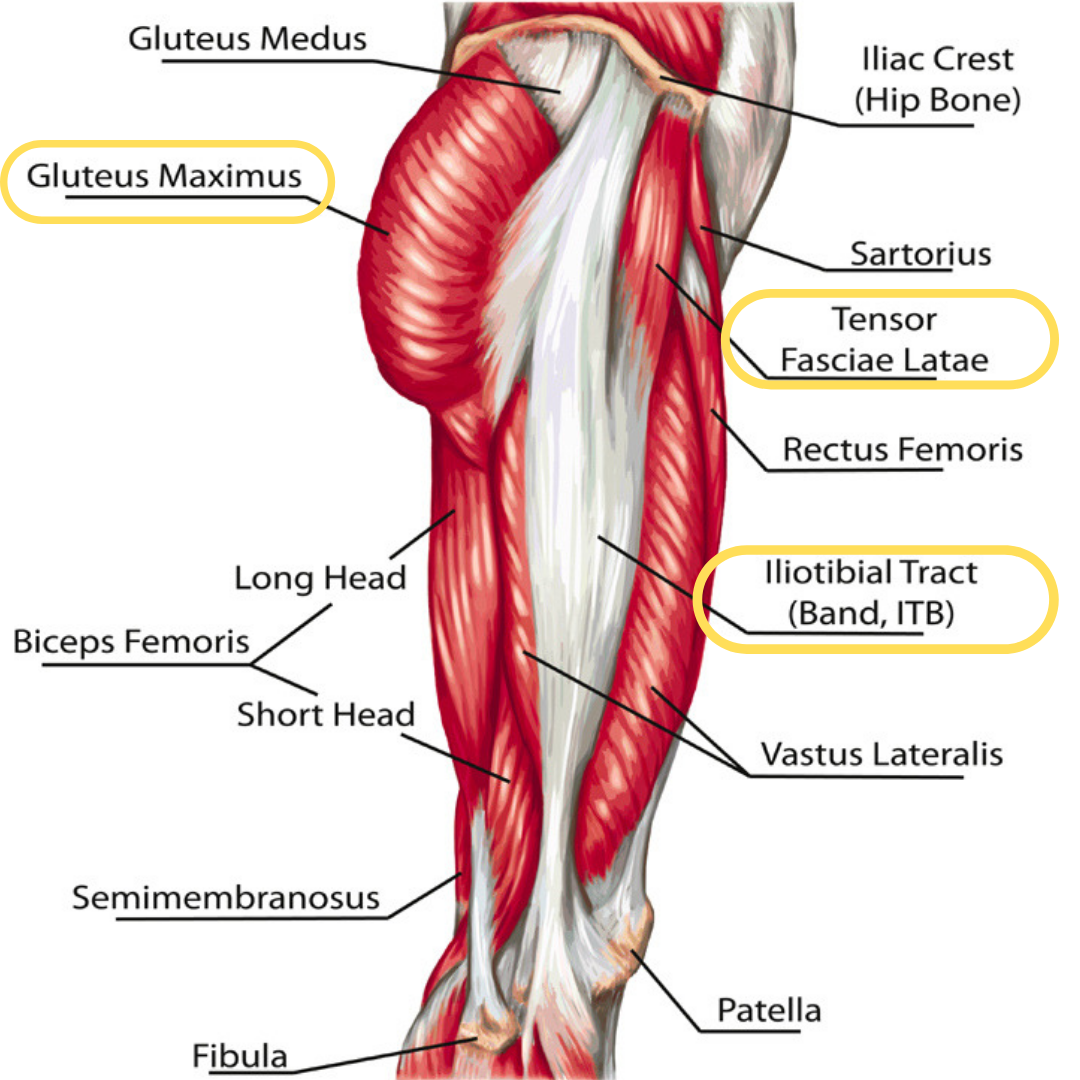
Insertion Points: Iliac Crest, Knee
Muscles Involved & To Know:
Tensor Fascia Latae
Gluteus Maximus
Gluteus Medius
The Iliotibial tract runs from the hip (iliac crest) to the knee with insertion on the tibia at Gerdy’s Tubercle (trivia!) and is believed to also span some fibers to the outside of the kneecap and head of the fibula. The IT band itself acts as a stabilizer of the lateral knee while also extending, abduct, and laterally rotate the hip when the associated muscles are functioning properly.
If you notice, the band itself is fibrous, meaning…
it is not designed to stretch.
Attention must be given to the muscles that make up and act on the IT band. Those would be the Tensor Fascia Latae (TFL) and the Gluteus Maximus (G. Max). If attention is not given to these essential muscles for running that are involved in stability, pelvic balance, and propulsion, they will slowly tighten up, eventually leading to a - multiple month long - process to rid yourself of the stabbing knee pain it can cause. We will discuss the biomechanics and how to address these muscles later in this series, but this is the basics that you must know to help relieve Iliotibial band pain while running. Focus on the muscles…not the band and the site of pain.
SIGNS, SYMPTOMS, & PREVALENCE
As described at the beginning of this article, Iliotibial Band Syndrome has a very distinct presentation of pain and discomfort. While the hip tightness is often not recognized, appreciated, or correlated until after we exam someone and describe the nature of their injury, the pain at the side of the knee is unmistakable. So that we have a more tangible understanding of this pain, here is a more succinct description.
sharp or burning pain at the lateral joint line of the knee.
How common is Iliotibial Band Syndrome? With injury prevalence in runners nearly 50% (Studies suggest 25-65%), IT Band Syndrome is the most common lateral knee injury.
IT Band Syndrome makes up nearly 15% off all running injuries.
Studies suggest it is slightly more common in male runners, new runners, and higher volume runners.
Clinical experience suggests it is one of the most common injuries runners present to a sports chiropractic office with.
Now that we have some understanding of the anatomy and prevalence of Iliotibial Band Syndrome in runners, we will progress our conversation to risks, common causes, and the biomechanics associated with ITBS.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Resolve Low Back Issues Part 6: Self-Care - What You Can Do For Low Back Pain
Over the last 5 weeks, we have discussed everything from what low back pain is, most common causes, some of the most common myths associated with low back pain, and when to consider imaging studies (x-ray, MRI, CT) due to red flags that lead us to something more severe being the cause. We even covered a few tips to help when you find yourself traveling for work or vacation.
We have been building up toward the actual care of low back pain but wanted to fully educate on how common low back pain is, what we know about low back pain at this time, and help you focus on life outside of back pain.
Low Back Pain Self-Care
Over the last 5 weeks, we have discussed everything from what low back pain is, most common causes, some of the most common myths associated with low back pain, and when to consider imaging studies (x-ray, MRI, CT) due to red flags that lead us to something more severe being the cause. We even covered a few tips to help when you find yourself traveling for work or vacation.
We have been building up toward the actual care of low back pain but wanted to fully educate on how common low back pain is, what we know about low back pain at this time, and help you focus on life outside of back pain.
Today, we are going to do just that.
When we look to decrease disability from low back pain and encourage and support patients back to an active lifestyle, this is done in two ways. EDUCATION & EXERCISE. We have already discussed the education component. Now it is time for exercise. Below are 5 ways to help manage and prevent your low back pain with exercise and stretching routines that can be done at home, the gym, or even at the office.
Side Bar -> If anyone gives you a hard time, or tosses a laugh in your way for stretching at the office, I will leave it up to you to either invite them to join (because they need to do this too), or, wait until they start having an issue with low back pain and then pass them our card! Seriously though, invite your co-works to join in, make it an office party, it will be fun.
Fix Your Low Back With These 5 Easy Exercises & Stretches You Can Do At Home or Work.
STEP 1: Get Out Of Bed With Our Morning Routine.
After a good night’s sleep, it is common for our muscles to want to remain in bed. Because of this, early morning activities can challenge our bodies more than they are ready to handle, resulting in a nice low back strain injury. If you are already dealing with low back pain, you know that morning stiffness can prevent you from even rolling over, not to mention actually get up out of said bed.
STEP 2: Desk Sitters - Get Up & Move
While things are improving, the seats we subject ourselves too in our cars, on the train, and at the office are just comfortable enough to keep you seated for an extensive period of time, but provide little support to keep you from tightening up in the process. Start this NOW -> Set an alarm on your phone that goes off every 1-2 hours. Walk around the office, hand-deliver a message, and then take 30 seconds and perform these stretches.
STEP 3: Pre-Workout Hip Mobility
We are going to assume you have a daily routine of some exercise? If you do not, reset, and start adding some exercise to your life, no other method is as impactful on helping your low back issues. Once you get to the gym, or home if you prefer, go through a GOOD HIP MOBILITY routine. We know that the more we improve the mobility of our hips, the less our low back has to work…overwork.
STEP 4: Post-Workout Core Strength
The same goes for core strength as hip mobility. The stronger our core, the less our low backs have to work. Now…I don’t mean getting down on the floor and performing a half-hearted set or some sorry excuse for crunch/sit-up type exercise. We are talking functional here. Planks, Side Planks, Plank Rolls, Heavy Farmer and Suitcase Walks, as well as The Big 3.
STEP 5: Strength For Life
Most people who have dealt with low back pain have since, and forever will, shy away from true strength movements. But let me just plug that as humans, you should be able to squat as well as pick something heavy off the ground without fear of hurting yourself. As you work on hip mobility and core strength, you have to start working in squats and dead-lifts. Start with these modifications and work on control and endurance.
Exercise is considered the best medicine for low back pain. While this is true and I strongly support this. Our actual goal with care is to get our patients back to these activities. But often, patients present in enough pain that they are unable to run, ski, bike, weight lift, etc. With that said, most can start with basic stretching and mobility until the pain is relieved. From there, exercise can prevent flair-ups, or at least decrease their intensity and length of the episode. Either way, low back pain has to have a component that includes YOU doing some, if not most, of the work.

Next week we will look at some of the traditional, as well as, new developments in conservative care low back pain. Until then, and if you are craving more reading, check out our ‘12 Ways..’ Tips guide to further help your low back pain.
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Cottonwood Heights Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Runner's Knee Bonus: Patellofemoral Pain Syndrome - Not Just For Runners
For several weeks we have been covering patellar femoral pain syndrome (PFPS), or runner’s knee as many like to call it. However, as with many of the conditions we see, it can be found in more than just one population of people. PFPS can also be caused by other physical activities that put repeated stress on the knee. This can include squatting, jumping, climbing stairs, etc. Along with that, PFPS can occur when you have patellar malalignment, which was touched on in Part 1 of our Runner’s Knee series.
With most PFPS we see, it comes from a sudden increase of load placed on the knee. So if you have recently increased your weight at the gym, time on the Stairmaster, or taken on a new activity, if the stress level on your knees has increased you could experience “runner’s knee” even if you do not consider yourself a runner. With that said, here are a few preventative measures we can implement that could help.
For several weeks, we have been covering patellofemoral pain syndrome (PFPS), or runner’s knee, as many like to call it. However, as with many of the conditions we see, it can be found in more than one population. PFPS can also be caused by other physical activities that put repeated stress on the knee. This can include squatting, jumping, climbing stairs, etc. Additionally, PFPS can occur with patellar malalignment, as touched on in Part 1 of our Runner’s Knee series.
Most PFPS we see come from a sudden increase in load on the knee. So if you have recently increased your weight at the gym, time on the StairMaster, or taken up a new activity, and the stress on your knees has increased, you could experience “runner’s knee” even if you do not consider yourself a runner. With that said, here are a few preventive measures we can implement to help.
PREVENTIVE TECHNIQUE #1:
If you are squatting, jumping, or having difficulty hiking or climbing stairs, ensure you get a proper warm-up. In addition to the treatment options listed in Part 3 of our Runner’s Knee series, you can perform band exercises before your activity. Each of these exercises is
beneficial in increasing our mobility and strength, as well as providing our bodies with proper preparation for the activities we engage in.
PREVENTIVE TECHNIQUE #2:
An additional preventive measure is to always use proper form. In all things we do, improper form can cause extra strain on our bodies. In all activities, especially lifting and squatting it is important that before we increase weight we ensure that our form is correct. Squatting with our knees in line with our toes, and our back naturally arched allows the weight to be properly distributed throughout, rather than having all the pressure on our knees.
PREVENTIVE TECHNIQUE #3:
The last preventive measure is simple but effective. It is important that we increase our training gradually and not all at once. If you are a lifter, gradually increase weight. If you are a hiker or climb stairs, increase your distance and pace gradually. Our bodies are adaptable, and with steady increase, it can adjust accordingly.
FINDING ANSWERS
So for those of us who are experiencing knee pain in the front of our knees and are not runners, there are answers here for us as well. It just so happens that those answers are very similar to those who run many miles a day. So don’t be afraid to dive into our multi-part series about runner’s knee. I think you will be able to find answers to your knee pain as well.
Check out the Part 1, Part 2, Part 3, and Part 4 of our Patellofemoral pain syndrome series here.
Janaye Freeman is a Certified Athletic Trainer & Lead Therapy Technician at Revive Sport & Spine in Murray, Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management for Murray, Holladay, Cottonwood Heights, Millcreek, Midvale, and Sandy.

Runner's Knee Part 4: Treatment, Rehabilitation, & Return To Running
After three exhilarating weeks of discussing Runner’s Knee, we have covered the anatomy, mechanism of injury, hip and ankle mobility, training modifications when injured, and self-care options. This week, we culminate with what happens when self-care is not enough, when you need to seek help, and what that looks like.
After three exhilarating weeks of discussing Runner’s Knee, we have covered the anatomy, the mechanism of injury, hip and ankle mobility, training modifications during injury, and self-care options. This week, we culminate with what happens when self-care is not enough, when you need to seek help, and what that looks like.
SEEKING HELP
When to seek care while dealing with patellofemoral pain is a common question we encounter. In all honesty, as runners, our natural tendency is to ‘wait & see’ and try to run the problem away. Furthermore, some will try to rest a week or two, putting training on hold, only to start running again and find the knee pain is still present.
Not to be all high and mighty, but in my professional opinion, the earlier you seek care, the less likely you are to lose precious training time, and the quicker we can get you over Runner’s Knee. To help simplify this, here are three rules to adhere to when debating care for your knee pain.
Knee pain is worsening with each run, earlier in the run, and lasting longer after each run causing your training to suffering.
Knee pain is not responding with consistent self-care and proper warm-up and cool-down routines.
Knee pain starts to be present during regular daily activities such as walking, taking the stairs, and rising from a chair.
WHAT DOES TREATMENT LOOK LIKE
So, you have decided to seek help with Runner’s Knee.
Step one: find a doctor who runs!
Now that step one is out of the way, let's talk about the basics of what actually happens and what you can expect from care in a sports medicine/chiropractic office.
To get us started, let's look at the hardest question first...How long will it take? That is a hard question to answer because every case is different. Each person presents with a different level of pain, unique exacerbations, varying training volume, intensity, and running age, as well as racing expectations and outlook on their condition. From all of that, nailing down an exact timeframe for peak performance is elusive. However, typical treatment plans range from 2 weeks to 2 months, again depending on goals and the time the condition has been present.
Once this is understood, the next step is to understand that this is a team effort. For most clinics, you will only be actively receiving care for 1-2 hours per week. What happens during the other 166 hours of the week is up to you, and we discussed that in our last article regarding self-care.
When an athlete presents to a clinic like ours, treatment should be a 3-tiered approach.
Soft Tissue: As we have reviewed the anatomy, we know that there is significant muscle ‘issues’ involved in runner’s knee. For this reason, this is where we start. How to decrease the tension and abnormal pull from muscles so that the patella tracks correctly and decreases joint wear is one part of the puzzle. There are numerous ways to achieve this and in our clinic, we find Dry Needling, Shockwave Therapy, IASTM - instrument-assisted soft tissue mobilization, and cupping therapies to provide the best, and quickest, results.
Joint Mobility & Stability: After the soft tissue is addressed, we look at the structure. As discussed in our second article, the mobility of the hip and ankle are vital to correcting and relieving runner’s knee pain. Manipulation is designed to restore normal motion to a joint that is currently not moving properly. Over time, restored joint motion can improve running mechanics and decrease strain and stress placed on the surrounding muscles.
Rehabilitation Exercise: Lastly, once we have the muscles and joints under control, a building back up must occur in two ways. One, we must create stability and control of the joint through muscle strength. Two, training volume must begin to ramp up, slowly and controlled, which we discussed in the third article of this series. To further address part one, rehabilitation exercises need to be explained and directed.
Below is a basic 3-phase rehabilitation program aimed at relieving patellofemoral pain while helping to rebuild strength and prevent future occurrences.
Phase 1: During the first phase of care, our exercise prescription is aimed at pain relief and improved mobility. These exercises should be performed 3-5 times per week, preferably as part of your running warm-up if we are able to continue training through care. We start with 1 set of 10 reps for each exercise and 30 seconds for the wall sit, working up to 2 sets over the course of this phase of care, which is typically 2-4 weeks.
Phase 2: The second phase of care focuses on returning to your full running volume while building strength and stability. We expect to perform these exercises 3-5 times per week again, preferably before running, but we will start with 1 set of 15 for each exercise and a 45-second hold for the wall sit. Over the 2-4 weeks of this phase, we will work up to 2 sets of each exercise.
Phase 3: The third phase focuses on strength and injury prevention. At this time, we move to self-care as the patient is released from active care. Our goal is to perform 2-3 sets of 10-15 reps for each exercise as a warm-up before each and every run.
RETURN TO RUNNING
Once we work through care and training is gradually ramping back up, or you have been consistent with home care, how do you know you are ready to return to full, unrestricted running? To help determine whether you can get back out there and get after it, we use our return-to-running assessment. Our goal here is to complete all five exercises without pain. In this assessment, each exercise must be completed for 60 seconds, with as many repetitions as possible.
Finally, we have covered more information than you could ever want to know about runner’s knee - patellofemoral pain syndrome. Hopefully this has been enough information to keep you out of our office, but... runners have many other issues and injuries to face, and Runner's Knee is but one of them. Until next time...
Train Smart, Recover Well, Race Great!
-Dr. Reheisse
Dr. Reheisse is a Board-Certified Chiropractic Sports Physician practicing in Murray, Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Runner's Knee Part 3: Training Modification & Self-Care
Over the last two weeks, we have discussed the ins and outs of what Patellofemoral Pain Syndrome is, the anatomy involved, how adjacent joints (hip and ankle) can lead to maltracking issues, and why runner’s are specifically susceptible to this common overuse injury. You can read Part 1 & Part 2 here.
Now it’s time to talk self-treatment and training modification. Our goal is to maintain training (load) if possible when you find Runner’s Knee settling in, but more times than not, rest and self-care is needed while also modifying our training volume and intensity until symptoms recede.
Over the last two weeks, we have discussed the ins and outs of Runner’s Knee - Patellofemoral Pain Syndrome, the anatomy involved, how adjacent joints (hip and ankle) can contribute to maltracking, and why runners are particularly susceptible to this common overuse injury. You can read Part 1 & Part 2 here.
Now it’s time to talk about self-treatment and training modification. Our goal is to maintain training (load) if possible when you find Runner’s Knee settling in, but more often than not, rest and self-care are needed while also modifying our training volume and intensity until symptoms recede.
TRAINING MODIFICATION FOR RUNNER'S KNEE
Let's get the big one out of the way first! One of the reasons many runners try to avoid visits to a doctor’s office about one pain or another is the fear that the physician will tell them to stop running. Depending on the injury, how long it has been ongoing, current severity, and other factors, some runners are able to continue training during treatment and rehab, albeit in modified form.
Without getting too technical, we first need to understand the concept of 'load' and how it changes when we are injured. As runners, we have a specific language, so I am going to explain it in those terms. When our training is on and we are injury-free and fit, long runs, speed work, tempo runs, and intervals go well and help us improve. The load on the knee (and other joints) is well managed, and there is ample time to recover. Now, let's say you decide to sign up for a race that is in 6 weeks, and your training base is less than optimal. In hopes of having a good race, you ramp up quickly, doing hard days back-to-back, pushing it to your goal race pace for a good portion of your long run, etc., and now...BOOM, knee pain! What has happened here is that you exceeded the load threshold your body can handle and recover from.
For an interesting read, look into Scott Dyes work. This is what is commonly referred to the ‘envelope of function’ in the coaching and physician world.
Jumping back in...now that we are injured, our load threshold is lower. This is why a 5-mile run is painful halfway through when just 2 weeks ago, you were cruising through 10 miles with a few pickups. If you continue down this path, patellofemoral pain can become so severe that just getting out of bed and navigating stairs is difficult. When we encounter a runner in this position, we need to sit down and talk about a training plan, race expectations, and our long-term goals.
While it is never our goal to shut a runner down in the middle of a training cycle, the athlete's long-term health and ability are top of mind. Because of this, when discussing training, we tend to cover three things.
Can we gradually ramp up training while continuing to respond to treatment?
When we begin treatment, we have to start with a baseline. That may be 2 miles, 5 miles, or No miles before the pain sets in. That is our starting spot. As we follow-through with the suggested treatment plan, this load threshold must also go up. Rarely does pain go from 100 to 0, meaning, the pain goes from beginning at mile 2, then mile 4, then we find ourselves back up to 8-10 miles with no pain. This is the progress we look for.
Initial volume should decrease by 50% for the first 2 weeks.
If you are coming to us for knee pain, make a conscious effort to dial it back for a few weeks. This allows you to keep training, but also a little more rest than normal while we get through the first few treatment session.
Intensity, or pain-provoking runs, need to take a full break until volume can increase without pain.
With runner’s knee, we find that the harder, hillier efforts cause the most problems. While we want to maintain load on the knee while we treat, easy runs are the plan for the first few weeks. Looking at what we just talked about with gradually ramping up, we need to make sure you can handle a good distance without pain before we start pounding out the speed-work and hill repeats. And this goes for downhill too!
SELF TREATMENT OPTIONS FOR RUNNER'S KNEE
Now that we have discussed training modification, what can you start doing at home to help with Runner’s Knee? Honestly, you should be doing all of this already, but pain is a much better reminder to break out the foam roller than a good run. Your relationship with your foam roller needs to be strong. Your diet needs to be on point. Your bedtime needs to be early. Lastly, you need to realize that weight training is your friend.
Let's discuss a few of the easiest and most common self-treatment options.
Foam Rolling:
I don’t need to further detail my love for foam rolling over stretch or the benefits that regular foam rolling can provide for a runner. As we address runner’s knee, rolling needs to be frequent, short bursts throughout the day. Meaning, roll the quadriceps, hamstrings, and posterior hip muscles 3-5 times per day. Again, these are short 2-3 minute sessions. 10-15 rolls up and down over each area. Check the video!
Hip Mobility Drills:
As runner’s, our knee functions is highly influenced and controlled by what is happening at the hip. If your hip range of motion is limited, this will eventually show up at the knee. Check the video!
Ankle Mobility Exercises:
As a practitioner, I’m typically a ‘ground-up’ person when it comes to runners. While the hip controls the show, if the ankle does not move properly, it can not react properly or efficiently when the foot hits the ground causing problems up the chain. Studies show that just a few degrees difference between ankles is a good indicator of future injury. Work on your ankle mobility - Check the video!
This is a bit controversial. As you will hear me say in the demonstration below, the effect of taping is hard to prove. Don’t get me wrong, I love taping, in the short-term. It is by no means a long term fix for any injury! With that, you can also find 500 runners at the upcoming Big Cottonwood Marathon or the St. George Marathon that have their knees, shins, hips, and ankles taped that will absolutely swear by it. With all of that, I just don’t have solid evidence that proves any of that...but placebo is a powerful tool and I do appreciate taping as a means to help someone recovery and cue good movement patterns. If anything, the tape is a visible reminder to roll, stretch, and rest more. Check the video!
Body-Mass Index:
BMI has to be briefly discussed her because whatever weight we are carrying around affects our knees! Remember from the part of this series we mentioned that during running, the knee takes on 5-6 x’s your body weight during each step. While many people us running for weight loss, and other avoid it due to weight, the fact is, those with knee pain will benefit from weight loss if they are in the higher BMI category. I am not a dietician, we do not push weight-loss in our office, and I can’t tell you how many ‘Clydesdales’ category runners that can kick my tail in a race. Health is more than just pounds, but Runner’s Knee can be helped by a better BMI.
Psychosocial Influences:
Lastly, psychosocial factors. Runner’s are among the worst when it comes to injuries and the doom and gloom that comes with it. Some are severe enough that I have referred out to a professional for guidance. This is not something to be ashamed of and can actually help your recovery and performance. We now understand pain a bit better than we did 20 years ago, we still have a long way to go, but we know one thing to be true, if you do not think you will get better, you won’t. You have to buy into the plan, think positive, take the little wins, and know that this will not last forever. Any injury will last longer than we want it to, but you have to realize that by pure running statistics, you will get hurt at some time if you are training consistently, but it will also pass.
Hopefully, this article cleared up a few things regarding your training and the ability to continue through treatment, as well as a few ways to care for Runner’s Knee yourself. Ideally, you can manage this yourself, learn from it, and prevent it from recurring. As runners, we are prone to injury; that is just the way it is. But, we want to make sure you have the necessary knowledge and tools to help yourself before you give up, stop running, and then drag yourself into a sports physician's office.
LET'S REVIEW TODAY’S INFORMATION
When faced with Runner's Knee, training modifications are a must. We typically cut the training volume by 50% and avoid intense workouts (intervals, hills, tempo) for the first 2 weeks.
Self-care is a must. It not only helps speed your recovery over your treatment plan, but it can also help prevent future injury.
Self-care can be as simple as foam rolling a few times per day or running specific mobility, stability, and strength exercises.
Stay tuned for part 4 of our runner’s knee series, where we will discuss when to seek treatment and how we treat Runner’s Knee in our office, as well as a few examples of our suggested rehabilitation exercises.
Train smart, recover well, race great!
Dr. Reheisse is a Board Certified Chiropractic Sports Physician practicing in Murray, Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.

Runner's Knee Part 2: Hip & Ankle Mobility - How It Relates To Patellofemoral Pain Syndrome
In part 1 of our runner’s knee series, we discussed the specific anatomy involved, how and why we experience pain over/in the front of the knee, and most importantly, how running, and specifically downhill running, can hasten your onset of patellofemoral pain syndrome. ->Read Part 1 Here <-
Today, in part 2, we are going to move away from the knee and look at the friendly joints above and below. As we know, and you will soon find out, the hip and the ankle are in control of the knee and more times than not, pain at the knee is caused by faulty mechanics, immobility, or strength and stability deficiencies at either or both of these joints. Read on!
In part 1 of our runner’s knee series, we discussed the specific anatomy involved, how and why we experience pain over/in the front of the knee, and most importantly, how running, and specifically downhill running, can hasten the onset of patellofemoral pain syndrome. ->Read Part 1 Here <-
Today, in part 2, we are going to move away from the knee and look at the friendly joints above and below. As we know, and you will soon find out, the hip and the ankle are in control of the knee, and more often than not, pain at the knee is caused by faulty mechanics, immobility, or strength and stability deficiencies at either or both of these joints. Read on!
HIP FUNCTION IN RUNNING AND ITS RELATION TO KNEE PAIN
So that we have a starting point, we are going to travel from the hip down. Mainly because it is more commonly the culprit of running-associated knee pain (my own clinical experience), but also because it is the bigger joint with more opportunity for complications.
To help explain how the hip acts on the knee, I commonly tell patients in the clinic that we have no ‘knee muscle’, but that everything controlling the knee comes from the hip. While this is not exactly true, we have some very important muscles, like the VMO and popliteus, that act strongly on the knee without originating from the hip. Hopefully, you can read through that and see my point here. Control at the knee is primarily governed by the hip.
When we encounter a runner with patellofemoral pain, we will ‘treat’ the knee… but the majority of our work is spent on improving hip mobility, strength, and stability. We find that issues here can lead to compensations, deficiencies, and imbalances that contribute to Runner’s Knee.
IT band tightness pulls on the patella causing it to track laterally, or to the outside.
Hip tightness can cause an anterior pelvic stance. This can inhibit and tighten the hamstrings causing an altered gait that is ‘quad heavy’. This tilt and tightening can lead to altered mechanics at the knee and also lead to patellofemoral pain.
Hip drop due to a weakness of the glute muscles can lead to what we are now calling the Miserable Malalignment Syndrome.
Let's talk about that last one for a minute as this is becoming more and more common in running associated knee pain. Miserable Malalignment Syndrome is the name now given to the cascading breakdown when the hip and ankle fail. Essentially, when our foot is planted, the glute medius muscle of the foot planted holds our pelvis level. When this weakens, the hip drops, causing the other side to respond. This response causes an inward rotation of the femur bone, an outward rotation of the tibia (shin bone) in an attempt to compensate, and lastly, a turning out of the foot resulting in a crashing in of the inside of the foot.
Guess which joint is in the middle taking all of that rotation torque?
I explain this in the video and picture below. Now, this condition got its name, not necessarily for runners, but for those who sit too much and exhibit the same pattern, but it fits here. If anything, this helps explain how important our hip mobility and strength is to the health of our knees. If you remember, as runners, we load the knee with 5-6 times our body weight with each and every step. Rotation in a joint NOT designed for rotation is destined to cause problems.
ANKLE FUNCTION IN RUNNING AND ITS RELATION TO KNEE PAIN

Now that we better understand the hip and its relation to knee pain, let's travel down the road a little to the ankle joint. Without getting into the kinematics of the ankle and the joints that make up this complex area of the body, let's just try to understand one thing...DORSIFLEXION.
Dorsiflexion is your ability to bring the top of your foot toward your shin. When we run, dorsiflexion allows us to strike the ground, react, and toe-off properly, pushing from our big and second toes. To help understand this, lets picture what poor dorsiflexion looks like. The next time you are walking around, look for someone who walks with their feet turned outward. What is usually happening here is that their hip tightness causes their posterior hip muscles (glutes, piriformis, etc.) to pull on the femur, resulting in an outward turned leg and foot. And...Unless they rode in on a horse, they are not walking with their kneecaps over their feet in this position which leads us to what we just discussed, the foot crashes inward, the kneecap points a different direction of the foot, and we now have pain. You can now imagine that there is no way this person is walking properly, meaning they are not actually toeing off correctly, but the inside of their foot, now...IMAGINE THIS PERSON RUNNING.
You may have realized that poor ankle dorsiflexion and the lack of hip mobility and stability can cause the same problem. The truth is, they tend to run together. While we will always treat any and all problems presented to us, it is my job to find the key that unlocks the whole system and more times than not, it is the hips!

TIME TO REVIEW WHAT WE LEARNED TODAY
Most of the muscular control of the knee comes from the hip. Lack of mobility and strength here can contribute to patellofemoral pain syndrome.
Lack of ankle dorsiflexion (the ability to bring the foot toward the shin) can cause outward rotation of the foot and undue rotational strain on the knee.
Issues at the hip and knee can lead to what we are now calling the Miserable Malalignment Syndrome. Essentially, when we run, our hips drop, causing an inward rotation of the femur, a counter-outward rotation of the shin bone, turning out of the foot, and caving in of the inner foot, leaving the stress on the knee.
To properly address runner’s knee, we must address these deficiencies at the hip and ankle.
Once you have digested the information we discussed in these last two articles, keep your eyes peeled for part 3 next week, as we will begin discussing what to do if you already have patellofemoral pain and when you should seek care so you can continue, or return to, training.
Dr. Reheisse is a Board-Certified Chiropractic Sports Physician practicing in Murray, Utah. Revive Sport & Spine provides evidence-supported chiropractic care and conservative sports injury management.